Herbal Remedies of Urinary Tract Infection – Causes, Symptoms, Diagnosis & Treatment

ABSTRACT

Urinary Tract Infection (UTI) is a condition that deserves attention because even a seemingly minor urinary complaint can sometimes develop into a more serious problem if ignored. Changes in urination, burning sensation, pelvic discomfort, urgency, or unusual urine appearance may indicate an underlying urinary infection. Women commonly experience UTIs, but no age group is completely protected. Maintaining adequate fluid intake, healthy personal hygiene, and proper urinary habits can help reduce the risk. Today, I would like to tell you about UTI in detail, including why it occurs, its common signs and symptoms, contributing factors, diagnostic methods, possible complications, and how it can be understood and managed through both modern medicine and Ayurveda.
 Urinary Tract Infection

INTRODUCTION

Urinary Tract Infection (UTI) is one of the most common infections affecting the urinary system and can involve the urethra, urinary bladder, ureters, or kidneys. It occurs when microorganisms, most commonly bacteria, enter and multiply within the urinary tract, leading to symptoms such as burning during urination, frequent or urgent urination, lower abdominal discomfort, cloudy or foul-smelling urine, and sometimes fever. Although UTIs can affect people of all age groups, they are particularly common among women. Recurrent or inadequately managed infections may progress to more serious conditions, including kidney involvement and systemic infection.

STATISTICS OF URINARY TRACT INFECTION

Urinary Tract Infection (UTI) is a widespread health problem, particularly among women. . More than 50% of adult women experience at least one UTI during their lifetime. Nearly 25% of women who develop a bladder infection may experience another episode, making recurrence a common concern. Women are affected much more frequently than men, largely due to anatomical differences that allow bacteria to reach the urinary tract more easily. UTI is one of the most commonly diagnosed bacterial infections in community and healthcare settings and contributes significantly to antibiotic use. The risk of UTI may increase with advancing age, especially when factors such as incomplete bladder emptying, urinary obstruction, or catheter use are present. Together, these statistics demonstrate the substantial burden of UTI and emphasize the importance of timely diagnosis, appropriate treatment, and preventive urinary care.

INTERESTING FACT ABOUT URINARY TRACT INFECTION

  • UTI can affect anyone: Although more common in women, urinary infections can occur in men, children, and older adults.
  • Bacteria are the usual cause: Most UTIs develop when bacteria from the surrounding area enter the urinary tract and multiply.
  • The bladder is commonly involved: Lower urinary tract infections often affect the bladder and are commonly referred to as cystitis.
  • Some UTIs have few symptoms: Certain people, particularly older adults, may not experience the typical burning or urinary urgency associated with infection.
  • Sexual activity can increase risk: In some women, sexual activity may facilitate the movement of bacteria toward the urethra.
  • Catheters can raise the risk: Urinary catheters provide a pathway through which microorganisms can enter the urinary system.
  • Kidney infections can develop: An untreated or complicated infection may travel from the bladder to the kidneys and require prompt medical attention.
  • Diagnosis is not based only on symptoms: Urine testing, particularly urinalysis and urine culture when indicated, can help identify infection and guide appropriate treatment.

CAUSES OF URINARY TRACT INFECTION

  • Bacterial entry: Most UTIs occur when bacteria from the skin or bowel region enter the urethra and multiply within the urinary tract.
  • Poor personal hygiene: Inadequate hygiene around the genital and urinary area can facilitate the transfer of microorganisms toward the urethra.
  • Insufficient fluid intake: Drinking too little water may result in less frequent urination, reducing the natural flushing of microorganisms from the urinary tract.
  • Holding urine for long periods: Repeatedly postponing urination can interfere with normal bladder emptying and may contribute to bacterial growth.
  • Sexual activity: Sexual intercourse can move bacteria toward the urethral opening, increasing the likelihood of infection in susceptible individuals.
  • Incomplete bladder emptying: Conditions that prevent the bladder from emptying completely can leave residual urine, creating an environment favorable for microbial multiplication.
  • Urinary obstruction: Kidney stones, enlarged prostate, or other blockages can interfere with urine flow and increase infection risk.
  • Urinary catheter use: Catheters can introduce microorganisms into the urinary tract and are an important risk factor for healthcare-associated UTIs.
  • Pregnancy: Physiological and hormonal changes during pregnancy can affect urinary flow and increase susceptibility to UTI.
  • Underlying health conditions: Diabetes and certain disorders affecting the urinary system or immune function can make a person more vulnerable to infection.

SIGN AND SYMPTOMS OF URINARY TRACT INFECTION

  • Burning while urinating: A burning, stinging, or painful sensation may occur during passage of urine.
  • Frequent urination: A person may feel the need to urinate more often than usual, even when only a small amount of urine is passed.
  • Sudden urinary urgency: There may be a strong and difficult-to-control urge to urinate.
  • Lower abdominal discomfort: Pressure, heaviness, cramps, or pain may be felt around the lower abdomen or pelvic region.
  • Changes in urine: Urine may appear cloudy or occasionally contain blood. An unusual or strong odor can also occur.
  • Incomplete emptying: Some individuals may feel that the bladder has not emptied completely after urination.
  • Fever and chills: These symptoms may occur when the infection is more significant or has involved the upper urinary tract.
  • Back or side pain: Pain in the lower back or side, particularly along with fever, may indicate possible kidney involvement.
  • Nausea or vomiting: These symptoms can accompany an upper urinary tract infection, especially when the kidneys are affected.
  • General weakness: Fatigue, reduced appetite, or a feeling of being unwell may accompany a more severe infection

DIAGNOSIS OF URINARY TRACT INFECTION

  • Medical history: The healthcare professional asks about urinary symptoms, their duration, previous infections, medications, pregnancy status, and relevant medical conditions.
  • Physical examination: An examination may be performed to identify abdominal, pelvic, flank, or other findings that could suggest urinary infection or another condition.
  • Urinalysis: A urine sample is examined for findings such as white blood cells, red blood cells, nitrites, and other indicators that may support the presence of infection.
  • Urine culture: The sample is grown in a laboratory to identify the causative microorganism and determine which antibiotics are likely to be effective. This is particularly useful in recurrent, complicated, or suspected upper urinary tract infections.
  • Urine microscopy: Microscopic examination can detect pus cells, bacteria, blood, and other urinary abnormalities that may help in evaluation.
  • Blood investigations: When a severe or upper urinary tract infection is suspected, tests such as a complete blood count and kidney function tests may be recommended.
  • Imaging studies: Ultrasound, CT, or other imaging may be considered when kidney stones, urinary obstruction, structural abnormalities, recurrent infections, or complications are suspected.
  • Pregnancy testing: In women of reproductive age, pregnancy assessment may be appropriate because pregnancy changes the evaluation and management of UTI.
  • Differential diagnosis: Similar symptoms can occur with vaginal infections, sexually transmitted infections, kidney stones, or bladder conditions, so these possibilities may need to be excluded.
  • Clinical assessment: The final diagnosis is made by combining the patient’s symptoms, examination findings, and appropriate laboratory investigations rather than relying on a single test alone.

MANAGEMENT OF URINARY TRACT INFECTION

  • Medical evaluation: Treatment should begin with proper assessment to determine whether the infection is uncomplicated, recurrent, or associated with kidney involvement or another underlying problem.
  • Appropriate antibiotics: When a bacterial UTI is diagnosed, antibiotics may be prescribed according to the type of infection, patient factors, local resistance patterns, and, when required, urine culture results.
  • Adequate hydration: Maintaining sufficient fluid intake can support normal urine production and help prevent dehydration. Fluid intake should be individualized in people with kidney, heart, or other conditions requiring fluid restriction.
  • Regular bladder emptying: Avoiding unnecessary or prolonged postponement of urination may support normal bladder function.
  • Pain and fever management: Suitable medicines may be recommended by a healthcare professional to relieve discomfort, fever, or urinary symptoms.
  • Identify underlying causes: Recurrent infections may require evaluation for factors such as urinary stones, obstruction, incomplete bladder emptying, diabetes, or other urinary tract abnormalities.
  • Catheter care: When a urinary catheter is necessary, appropriate insertion and maintenance practices can help reduce the risk of catheter-associated infection.
  • Special attention during pregnancy: UTIs during pregnancy require timely medical assessment because untreated infection can lead to complications for the mother and pregnancy.
  • Management of kidney infection: Fever, chills, vomiting, or pain in the back or side may indicate upper urinary tract involvement and require prompt medical care.
  • Complete prescribed treatment: Patients should follow the prescribed treatment schedule and seek medical advice if symptoms persist, worsen, or return after treatment rather than self-medicating repeatedly.

AYURVEDIC INSIGHTS OF URINARY TRACT INFECTION

From an Ayurvedic perspective, Urinary Tract Infection (UTI) does not have a direct one-to-one equivalent disease name, but its clinical presentation can be correlated with disorders of Mutravaha Srotas (urinary channels), particularly Mutrakrichra, which is characterized by painful or difficult urination. The condition may involve predominantly Pitta and Vata Dosha, especially when burning sensation, pain, frequent urination, and altered urinary function are present. Ayurvedic literature describes Basti (urinary bladder) and Vankshana (groin region) as important sites associated with the Mutravaha Srotas( urinary carrying channel) and disturbance of these channels may result in abnormal urinary function. Dietary and lifestyle factors such as excessive intake of pungent, sour, salty, and heat-producing foods, inadequate fluid intake, suppression of the urge to urinate, excessive physical exertion, and impaired digestion may contribute to Dosha imbalance and urinary disturbances. Ayurveda emphasizes Nidana Parivarjana (avoidance of causative factors), correction of Agni(digestive fire),appropriate hydration, and maintenance of Mutravaha Srotas function( urinary  carry channels). Traditionally described urinary-supportive herbs include Gokshura (Tribulus terrestris), Punarnava (Boerhaavia diffusa), Varuna (Crataeva nurvala).

1. Ashtanga Hridaya – Nidana Sthana 9/4

बस्तिवङ्क्षणमेढ्रार्तियुक्तोऽल्पाल्पं मुहुर्मुहुः ।
मूत्रयेद्वातजे कृच्छ्रे पैत्ते पीतं सदाहरुक् ॥

This description explains that in Vataja Mutrakrichra, urination may occur frequently in small quantities with pain around the bladder, groin, and genital region, whereas Pittaja Mutrakrichra is associated with yellow urine and burning or painful urination. These features show a clinical resemblance to some manifestations of lower urinary tract infection.

2. Ashtanga Hridaya – Nidana Sthana 9/5

रक्तं वा कफजे बस्तिमेढ्रगौरवशोफवान् ।
सपिच्छं सविबन्धं च सर्वैः सर्वात्मकं मलैः ॥

This verse describes the involvement of Kapha in Mutrakrichra through features such as heaviness, swelling, and slimy or altered urine, while involvement of all three Doshas produces a mixed clinical presentation.

SAMPRAPTI (PATHOGENESIS) OF URINARY TRACT INFECTION

Nidana (Causative Factors)
↓
Viruddha / Ahitakara Ahara & Vihara (unsuitable diet and lifestyle) + Vegadharana (suppression of natural urinary urge)
↓
Agni Dushti (disturbance of digestive and metabolic function)
↓
Ama Nirmana (formation of incompletely processed metabolic waste)
↓
Dosha Prakopa — predominantly Pitta and Vata
↓
Mutravaha Srotas Dushti (disturbance of urinary channels)
↓
Srotorodha / Margavarodha (impaired urinary flow)
↓
Mutra Dushti (alteration in normal urinary function)
↓
Daha + Mutrakricchra + Mutraghata-like Features
(burning, painful or difficult urination)
↓
Local Inflammatory Response
↓
UTI-like Clinical Manifestations
↓
Repeated or Persistent Infection → Possible Upper Urinary Tract Involvement

HERBAL REMEDIES BY PLANET AYURVEDA FOR URINARY TRACT INFECTION

Planet Ayurveda is a well-established Ayurvedic healthcare organization that works to promote the ancient knowledge of Ayurveda through natural remedies and holistic health solutions. The company develops a wide range of herbal formulations using pure, high-quality ingredients and standardized herbal extracts, with a focus on maintaining safety, authenticity, and effectiveness. Following the principles of classical Ayurveda, Planet Ayurveda aims to support overall health by addressing the underlying causes of health concerns and encouraging balance in the body, mind and emotions. With an emphasis on quality, natural ingredients, and traditional approaches supported by modern research, the organization works toward making Ayurvedic wellness solutions available globally. We will explore various herbal approaches used for the management of Urinary Tract Infection according to Ayurvedic principles. The herbal formulations are;

  1. Punarnava Capsules
  2. Gokshuradi  Guggal
  3. Varunadi Vati
  4. Chandanadi Vati
  5. Reno Plan Syrup

Herbal Remedies of Urinary Tract Infection

Buy Now Herbal Remedies of Urinary Tract Infection

Buy Now Herbal Remedies of Urinary Tract Infection

PRODUCT DESCRIPTION

Punarnava Capsules

These capsules are prepared using Punarnava (Boerhaavia diffusa) is traditionally valued for supporting Mutravaha Srotas (urinary system) and promoting healthy urinary function. Its traditionally described Mutrala (diuretic) and Shothahara (supporting reduction of swelling/inflammation) properties make it relevant as a supportive herbal option in urinary complaints.

Dosage– 2 Capsules twice a day with  luke warm water after  a meal

Gokshuradi Gugga

Gokshuradi Guggulu is a classical Ayurvedic formulation traditionally used for disorders involving the Mutravaha Srotas (urinary channels). Planet Ayurveda’s formulation contains Gokshura (Tribulus terrestris), Shuddha Guggulu (Commiphora mukul), Maricha (Piper nigrum), Shunthi (Zingiber officinale)and many more herbs.Gokshura is traditionally valued for its Mutrala( diuretics) action and support of normal urinary flow, while Guggulu and the accompanying herbs provide complementary properties relevant to urinary discomfort and Srotas function.

Dosage-2 tablets twice a day with water after a meal

Varunadi Vati

It is an Ayurvedic formulation traditionally used to support healthy urinary function and may be considered as supportive management in UTI-related urinary complaints. Its key herbs include Varuna (Crataeva nurvala), Gokshura (Tribulus terrestris), and Punarnava (Boerhaavia diffusa) etc. Varuna is traditionally valued for supporting normal urinary flow, while Gokshura is known for its Mutrala (urinary-supportive) properties. Punarnava is traditionally described as Mutrala and Shothahara (supportive in swelling and inflammation). Together, these herbs may support urinary comfort and healthy Mutravaha Srotas function.

Dosage-2 tablets twice a day with water after a meal

Chandanadi Vat

Chandanadi Vati is a classical Ayurvedic polyherbal formulation traditionally used for urinary complaints. Its ingredients include Safed Chandan (Santalum album), Gokshura (Tribulus terrestris), Rasaut (Berberis aristata) and  many more herbs. Safed Chandan is traditionally valued for its Sheeta (cooling) and Pitta-pacifying properties, while Gokshura supports healthy urinary flow. Rasaut and the other herbs provide complementary traditional properties for urinary tract comfort.

Dosage-2 tablets twice a day with water after a meal

Reno Plan Syrup

It is an Ayurvedic herbal formulation used as supportive care for urinary and renal health. Its key ingredients include Punarnava (Boerhaavia diffusa), Gokshura (Tribulus terrestris), Bhumi Amla (Phyllanthus niruri), and  many more herbs. Punarnava and Gokshura are traditionally valued for their Mutrala (supporting healthy urine flow) properties, while Bhumi Amla .

Dosage-2 tsp twice a day with lukewarm water after a meal.

CONCLUSION

Urinary Tract Infection (UTI) is a common urinary disorder that requires timely attention because an untreated infection may extend from the bladder to the kidneys and lead to serious complications. Proper diagnosis through clinical assessment and appropriate urine investigations helps guide treatment, while confirmed bacterial infections may require suitable antimicrobial therapy. From an Ayurvedic perspective, UTI-related symptoms can be understood through disorders of Mutravaha Srotas (urinary channels), particularly conditions described under Mutrakrichra(painful urination) where disturbed Doshas, impaired Agni(digestive fire), inappropriate Ahara-Vihara, and suppression of natural urinary urges may contribute to urinary discomfort. Ayurvedic management emphasizes Nidana Parivarjana (avoiding causative factors), Agni( digestive fire) maintenance, adequate hydration, healthy urinary habits, and appropriate herbal support according to individual Prakriti and clinical presentation.

Ayurvedic Management of Urethrovaginal Fistula

Abstract

Urethrovaginal fistula (UVF) is an abnormal epithelialized tract connecting the urinary urethra and the vagina, resulting in continuous, involuntary leakage of urine. This debilitating condition often leads to significant physical discomfort, recurrent urogenital infections, and profound psychological distress. While conventional management relies heavily on surgical repair, patients frequently seek complementary and holistic approaches to support tissue healing, reduce local inflammation, and enhance overall urogenital resilience.
In traditional medical frameworks such as Ayurveda, urinary and vaginal disorders are interpreted through the lens of Mutravaha Srotas (urinary system) dysfunction, involving the deep aggravation of Vata and Pitta doshas, localized tissue depletion (Dhatu Kshaya), and accumulation of metabolic impurities (Ama). Ayurvedic management focuses on Vata-pacifying therapies (Vatashamana), tissue-rejuvenating botanicals (Rasayana), and formulations that promote wound healing (Vranaropana) and anti-inflammatory action (Shothahara). This article explores the comprehensive causes, clinical manifestations, diagnostic approaches, conventional interventions, and the targeted Ayurvedic management of urethrovaginal fistula using specific herbal formulations including Kaishore Guggul, Neem capsules, Ashwagandha capsules, Tribulus Power, and Boswellia Curcumin.

Urethrovaginal Fistula

Introduction

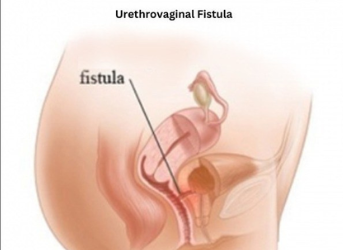
Urethrovaginal fistula represents a challenging clinical entity within urology and gynecology, characterized by an abnormal communication between the urethral lumen and the vaginal canal. This anatomical defect disrupts normal urinary continence, causing persistent, involuntary urine leakage into the vagina, which can result in severe perineal dermatitis, chronic vulvovaginitis, and social isolation.
The pathogenesis of UVF is commonly linked to obstetric trauma during prolonged or obstructed labor, gynecological or urological surgeries (such as urethral diverticulectomy or anterior vaginal wall repair), pelvic radiation therapy, chronic catheterization, or localized trauma and malignancies. While anatomical closure via surgical intervention remains the cornerstone of conventional treatment, postoperative complications, tissue fibrosis, or delayed healing often necessitate supportive and regenerative care.
Integrating Ayurvedic principles into the care continuum offers a holistic perspective aimed at strengthening local tissues (Mamsa and Shukra/Artava Dhatu), modulating chronic inflammatory responses, and improving local circulation to optimize tissue healing environments.

Causes

The etiology of Encapsulating Peritoneal Sclerosis is categorized into secondary forms (most common) and idiopathic primary forms:

  • Obstetric Trauma: Prolonged or obstructed labor leading to ischemic necrosis of the vesicovaginal and urethrovaginal septum remains a leading cause in developing regions.
  • Iatrogenic Injuries: Complications arising from pelvic surgeries, including vaginal hysterectomy, anterior colporrhaphy, urethral diverticulectomy, sling procedures for urinary incontinence, and transurethral interventions.
  • Radiation Therapy: Pelvic irradiation for gynecological malignancies causes microvascular obliteration, tissue ischemia, and delayed fistula formation.
  • Infections and Inflammation: Severe chronic urinary tract infections, untreated pelvic inflammatory disease, or foreign bodies (such as eroded synthetic meshes or long-term indwelling catheters).
  • Malignancy and Trauma: Direct invasion by urogenital tumors or penetrating pelvic trauma.

Signs and Symptoms

The clinical presentation of urethrovaginal fistula is distinct and significantly impacts a patient’s quality of life:

  • Continuous Urinary Incontinence: Involuntary, constant leakage of urine into the vagina, independent of physical exertion or bladder fullness.
  • Recurrent Urogenital Infections: Frequent urinary tract infections (UTIs) and persistent vaginitis due to constant moisture and altered local pH.
  • Local Irritation and Dermatitis: Chronic excoriation, burning, pruritus, and excoriation of the vulvar and perineal skin due to prolonged exposure to urine.
  • Psychosocial Distress: Significant anxiety, depression, and social withdrawal resulting from continuous leakage and malodor.
  • Dyspareunia: Pain or discomfort during sexual intercourse secondary to scar tissue formation and localized inflammation.

Investigations

Accurate anatomical localization and sizing of the fistula tract are essential for determining the appropriate management strategy:

  • Clinical Examination: Comprehensive pelvic and speculum examination, often utilizing a double-speculum or methylene blue dye test to visualize the fistulous opening along the anterior vaginal wall.
  • Cystourethroscopy: Direct visualization of the urethral mucosa to identify the internal opening of the fistula relative to the bladder neck and external urethral meatus.
  • Imaging Studies: Voiding cystourethrography (VCUG), retrograde urethrogram (RUG), or pelvic magnetic resonance imaging (MRI) to delineate the exact tract anatomy and assess surrounding tissue health.
  • Urodynamic Studies: Performed to evaluate baseline bladder storage, compliance, and sphincter function prior to planning definitive closure.

Management

Conventional management of urethrovaginal fistula primarily revolves around surgical reconstruction, though conservative measures may be attempted in very small, acute, or early-stage fistulae.

  • Conservative Measures: Continuous bladder drainage via an indwelling Foley catheter for 4 to 6 weeks, combined with management of local infections and estrogen therapy in postmenopausal women to promote mucosal healing.
  • Surgical Repair: Transvaginal or transabdominal surgical excision of the fistulous tract with multi-layered closure and healthy tissue interposition (such as a Martius flap or labial fat pad) to ensure tension-free healing.
  • Supportive and Regenerative Care: Postoperative wound care, infection control, and complementary herbal protocols to enhance tissue regeneration and reduce localized inflammation.

Ayurvedic View and Management

In Ayurveda, urethrovaginal fistula can be understood through the disruption of Mutravaha Srotas (channels of urine transportation) and Artavavaha Srotas (female reproductive channels). The fistulas are known as Bhagandar in Ayurveda. The condition manifests due to deep-seated Vata and Pitta dosha aggravation combined with Dhatu Kshaya (tissue depletion) and localized obstruction or structural trauma (Sanga and Vrana).
When Vata is vitiated, it causes dryness, pain, and degeneration, while aggravated Pitta introduces heat, inflammation, and potential suppuration or chronic unhealed ulceration (Dushta Vrana). Ayurvedic management focuses on Vatashamana (pacifying Vata), Raktashodhana (purifying blood and microcirculation), Shothahara (anti-inflammatory action), and Vranaropana (wound healing and tissue regeneration).

Ayurvedic Formulations for Urogenital Health

Planet Ayurveda provides authentic, high-quality herbal formulations crafted in GMP-certified facilities using standardized extracts. Free from synthetic additives, chemicals, and heavy metals, these products support holistic healing and tissue recovery.

The specific protocol suggested for the management of Urethrovaginal Fistula includes:

  1. Kaishore Guggul
  2. Neem Capsules
  3. Ashwagandha Capsules
  4. Tribulus Power
  5. Boswellia Curcumin

Care Pack of Urethrovaginal Fistula

Buy Now Care Pack Urethrovaginal Fistula

Buy Now Care Pack Urethrovaginal Fistula

PRODUCT DESCRIPTION

1. Kaishore Guggul

A classical herbal powder blend formulated with potent diuretic and renal-protective botanicals, including Punarnava (Boerhavia diffusa), Gokshura (Tribulus terrestris), Varun (Crataeva nurvala), and Shigru (Moringa oleifera). While traditionally utilized for urinary health, its deep-acting diuretic and anti-inflammatory properties help reduce abdominal fluid accumulation (ascites), alleviate tissue edema, and promote the clearance of metabolic wastes and toxic fluid collections from the peritoneal cavity.

Dosage: 2 tablets twice daily, with plain water after meals.

2. Neem Capsules

Formulated with standardized extracts of rejuvenative and detoxifying herbs designed to support internal fluid dynamics and cellular cleansing. Nephralka assists in regulating fluid balance, soothing irritated internal membranes, and supporting the body’s natural mechanisms for filtering metabolic byproducts, thereby reducing the toxic burden on deep visceral tissues.

Dosage: 2 capsules twice daily, with plain water after meals.

3. Ashwagandha Capsules

Prepared from the extracts of Pinus roxburghii (Chir Pine / Saral), this traditional preparation possesses strong Lekhana (scraping), antimicrobial, and deep tissue-cleansing properties. In conditions characterized by abnormal fibrous tissue deposition and encasement, Saral helps break down stubborn adhesions, stimulates microcirculation, and supports the reduction of dense, sclerotic tissue formations within the body.

Dosage: 1 capsule twice daily, with plain water after meals.

4. Tribulus Power

Containing equal proportions of three classical fruits—Amalaki (Emblica officinalis), Bibhitaki (Terminalia bellirica), and Haritaki (Terminalia chebula). Triphala is celebrated as the ultimate tridoshic balancer and gentle internal cleanser. It aids in deep detoxification (Ama pachana), promotes regular bowel motility without causing irritation, supports optimal gastrointestinal tract health, and enhances nutrient absorption during recovery.

Dosage: 1 capsule twice daily, with plain water after meals.

5. Boswellia Curcumin

A classic Ayurvedic herbal powder blend containing pungent and cooling herbs such as Trivrit (Operculina turpethum), Pippali (Piper longum), Maricha (Piper nigrum), Shunti (Zingiber officinale), and cloves. Avipattikar Churna is exceptionally effective in balancing gastric acidity, stimulating sluggish digestive fire (Agni), clearing obstruction in the gastrointestinal tract, and promoting mild, natural bowel cleansing to relieve abdominal bloating and discomfort.

Dosage: 1 capsule twice daily, with plain water after meals.

Conclusion

Urethrovaginal fistula is a complex urogenital condition that severely impacts physical comfort and emotional well-being. While conventional surgical intervention remains essential for anatomical correction, integrating traditional Ayurvedic principles offers a comprehensive, supportive dimension to patient care. By addressing underlying doshic imbalances, purging metabolic toxins (Ama), reducing local inflammation, and nourishing depleted tissues (Rasayana), targeted herbal protocols—such as Kaishore Guggul, Neem, Ashwagandha, Tribulus Power, and Boswellia Curcumin—help create an optimal internal environment for tissue regeneration, infection control, and long-term urogenital health.

Ayurvedic Management of Encapsulating Peritoneal Sclerosis

Abstract

Encapsulating peritoneal sclerosis (EPS), sometimes referred to colloquially as “abdominal cocoon syndrome,” is a rare, severe, and potentially life-threatening condition characterized by a thick, fibrocollagenous membrane enveloping the small intestine and viscera. This progressive encasement leads to recurrent or complete intestinal obstruction, abdominal pain, malnutrition, and significant morbidity. While long-term peritoneal dialysis, prior abdominal surgeries, and chronic peritoneal inflammation are primary triggers, etiopathogenesis remains complex and challenging to manage through conventional interventions alone, which often alternate between conservative nutritional support and high-risk surgical adhesiolysis or enterolysis.

In Ayurveda, deep-seated fibrotic disorders involving structural encapsulation, chronic localized obstruction, and visceral congestion are interpreted through the lens of severe Kapha and Vata dosha aggravation, coupled with deep metabolic impairment (Agnimandya), accumulation of deep-seated toxins (Ama), and progressive vitiation of the tissue channels (Srotorodha). Modern medical management emphasizes nutritional optimization, anti-inflammatory pharmacotherapy (such as tamoxifen or corticosteroids), and careful surgical lysis when indicated. Complementary Ayurvedic protocols aim to dissolve fibrous tissue adhesions (Lekhana), correct metabolic fire, clear lymphatic and channel blockages (Srotoshodhana), and pacify aggravated Vata-Kapha doshas. This article explores the comprehensive causes, clinical manifestations, diagnostic criteria, conventional management strategies, and the targeted Ayurvedic perspective of Encapsulating Peritoneal Sclerosis utilizing specialized herbal formulations including Mutrakrichantak Churna, Nephralka Capsules, Saral Ghan Vati, Triphala Capsules, and Avipattikar Churna

Encapsulating Peritoneal Sclerosis

Introduction

Encapsulating peritoneal sclerosis is classified among the most challenging complications of peritoneal biology, most notably associated with long-term peritoneal dialysis (PD), though idiopathic forms (abdominal cocoon syndrome) also occur in adolescent or adult populations without a history of dialysis. The condition is defined by the formation of a dense, fibrous collagenous cocoon-like membrane that wraps around loops of the small intestine, restricting normal peristalsis and resulting in mechanical bowel obstruction.
The pathogenesis involves a multi-stage inflammatory and profibrotic cascade. Initial peritoneal injury—whether from bioincompatible dialysis solutions, recurrent peritonitis, chemical irritation, or surgery—triggers a chronic inflammatory response. Mesothelial cells undergo epithelial-to-mesenchymal transition (EMT), transforming into profibrotic fibroblasts that lay down extensive extracellular matrices and collagen. This continuous fibrogenesis creates a thick fibrous membrane that chokes the bowel, leading to failure to thrive, severe protein-energy malnutrition, recurrent nausea, vomiting, and bowel ischemia. Because conventional treatments carry high recurrence and surgical complication rates, exploring integrative, antifibrotic, and metabolic-cleansing strategies is of paramount clinical interest.

Causes

The etiology of Encapsulating Peritoneal Sclerosis is categorized into secondary forms (most common) and idiopathic primary forms:

  • Long-Term Peritoneal Dialysis (Secondary EPS): The duration of peritoneal dialysis is the single strongest risk factor. Exposure to bioincompatible dialysates (high glucose concentration, lactate buffers, advanced glycation end-products) causes cumulative peritoneal damage.
  • Recurrent Peritonitis Episodes: Severe or repeated bacterial and fungal peritonitis accelerates peritoneal membrane fibrosis and structural remodeling.
  • Prior Abdominal Surgeries and Trauma: Past surgical procedures, intraperitoneal hemorrhage, or trauma can provoke localized or generalized fibrous reactions.
  • Drug-Induced Triggers: Certain intraperitoneal antiseptics, beta-blockers (such as practolol, historically), and chronic use of mineral oils have been implicated in inducing sclerosing peritonitis.
  • Idiopathic (Abdominal Cocoon Syndrome): Occurring predominantly in young adolescent females from tropical or subtropical regions, this form may be related to congenital developmental anomalies of the peritoneum or sub-clinical retrograde peritonitis.
  • Autoimmune and Systemic Conditions: Systemic lupus erythematosus, sarcoidosis, and chronic intraperitoneal inflammation associated with malignancies can precipitate fibrotic encapsulation.

Signs and Symptoms

The clinical presentation of EPS typically mirrors subacute or chronic intestinal obstruction, often evolving insidiously:

  • Recurrent Abdominal Pain and Cramping: Diffuse, colicky abdominal discomfort exacerbated by eating, resulting from impaired peristalsis and bowel stretching against the rigid cocoon.
  • Gastrointestinal Dysfunction: Persistent nausea, recurrent vomiting, early satiety, anorexia, and alternating episodes of constipation or diarrhea.
  • Palpable Abdominal Mass: In advanced cases, a distinct, firm, irregular abdominal mass or encapsulated fullness may be palpated upon physical examination.
  • Severe Malnutrition and Weight Loss: Profound cachexia, muscle wasting, and hypoalbuminemia due to chronic malabsorption, protein-losing enteropathy, and fear of eating (sitophobia).
  • Features of Intestinal Obstruction: Episodes of acute-on-chronic complete bowel obstruction characterized by abdominal distension, absence of flatus, and visible peristalsis.

Investigations

Diagnosing Encapsulating Peritoneal Sclerosis requires a high index of suspicion, combining clinical history with advanced imaging and diagnostic modalities:

  • Contrast-Enhanced Computed Tomography (CT) Scan: The gold standard imaging modality. CT findings include peritoneal thickening, peritoneal calcification, loculated fluid collections, bowel wall thickening, tethering and conglomeration of small bowel loops encased in a membrane, and signs of mechanical obstruction.
  • Plain Abdominal Radiographs: May reveal signs of small bowel obstruction, multiple air-fluid levels, or characteristic intraperitoneal linear calcifications.
  • Diagnostic Laparoscopy or Exploratory Laparotomy: Direct visualization of the thick, fibrous cocoon encasing the intestine provides definitive diagnosis when imaging is inconclusive, though invasive.
  • Laboratory Blood Panels: Complete blood counts (assessing for anemia of chronic disease), serum albumin and total protein (evaluating malnutrition), inflammatory markers (CRP, ESR), and renal function tests to monitor baseline systemic status.

Management

Management of EPS requires a multidisciplinary approach balancing nutritional rehabilitation, medical antifibrotic therapy, and surgical intervention:

  • Nutritional Support: Initiation of total parenteral nutrition (TPN) to rest the bowel, correct severe malnutrition, and improve metabolic status before any intervention.
  • Medical and Pharmacological Therapy: Discontinuation of peritoneal dialysis and transition to hemodialysis. Use of immunosuppressants (corticosteroids) and antifibrotic agents (such as tamoxifen) to inhibit fibroblast proliferation and collagen deposition during early or mild inflammatory phases.
  • Surgical Intervention: Enterolysis and surgical peeling or resection of the thick peritoneal membrane to free the incarcerated bowel loops. Surgery is technically demanding and reserved for patients with clear mechanical obstruction refractory to conservative care.
  • Supportive Care: Management of fluid and electrolyte imbalances, pain control, and prevention of catheter-related sepsis.

Ayurvedic View and Management

In Ayurveda, Encapsulating Peritoneal Sclerosis can be conceptualized through the profound vitiation of Kapha and Vata doshas acting upon Mamsa, Meda, and Rakta Dhatu within the abdominal cavity (Koshtha). The pathological process aligns with severe Srotorodha (channel obstruction), Granthi or Arbuda formation (abnormal growths and fibrous encapsulation), and deep metabolic stagnation (Agnimandya).
When Vata is deranged, it drives abnormal tissue drying, erratic movement, and colicky pain, while vitiated Kapha contributes heaviness, coldness, dense mucous secretions, and excessive fibrocollagenous deposition. The accumulation of toxic metabolic byproducts (Ama) combined with stagnant tissue fluids creates a rigid, localized barrier. Ayurvedic management strategy focuses on Lekhana (scraping and reducing excessive fibrous tissues), Srotoshodhana (clearing and opening blocked microchannels), Deepana-Pachana (igniting digestive fire and digesting toxins), and Vatashamana (pacifying Vata to relieve spasms and pain).

Ayurvedic Formulations for Internal Cleansing and Fibrosis Management

Planet Ayurveda provides authentic, high-quality herbal formulations crafted in GMP-certified facilities using standardized extracts. Free from synthetic additives, chemicals, and heavy metals, these products support holistic healing and metabolic recovery.
The specific protocol suggested for the management of Encapsulating Peritoneal Sclerosis includes:

  1. Mutrakrichantak Churna
  2. Nephralka Capsules
  3. Saral Ghan Vati
  4. Triphala Capsules
  5. Avipattikar Churna

Herbal Remedies of Encapsulating Peritoneal Sclerosis

Buy Now Herbal Remedies of Encapsulating Peritoneal Sclerosis

Buy Now Herbal Remedies of Encapsulating Peritoneal Sclerosis

PRODUCT DESCRIPTION

1. Mutrakrichantak Churna

A classical herbal powder blend formulated with potent diuretic and renal-protective botanicals, including Punarnava (Boerhavia diffusa), Gokshura (Tribulus terrestris), Varun (Crataeva nurvala), and Shigru (Moringa oleifera). While traditionally utilized for urinary health, its deep-acting diuretic and anti-inflammatory properties help reduce abdominal fluid accumulation (ascites), alleviate tissue edema, and promote the clearance of metabolic wastes and toxic fluid collections from the peritoneal cavity.

Dosage: 1 teaspoon twice daily, with plain water after meals.

2. Nephralka Capsules

Formulated with standardized extracts of rejuvenative and detoxifying herbs designed to support internal fluid dynamics and cellular cleansing. Nephralka assists in regulating fluid balance, soothing irritated internal membranes, and supporting the body’s natural mechanisms for filtering metabolic byproducts, thereby reducing the toxic burden on deep visceral tissues.

Dosage: 1 capsule twice daily, with plain water after meals.

3. Saral Ghan Vati

Prepared from the extracts of Pinus roxburghii (Chir Pine / Saral), this traditional preparation possesses strong Lekhana (scraping), antimicrobial, and deep tissue-cleansing properties. In conditions characterized by abnormal fibrous tissue deposition and encasement, Saral helps break down stubborn adhesions, stimulates microcirculation, and supports the reduction of dense, sclerotic tissue formations within the body.

Dosage: 2 tablets twice daily, with plain water after meals.

4. Triphala Capsules

Containing equal proportions of three classical fruits—Amalaki (Emblica officinalis), Bibhitaki (Terminalia bellirica), and Haritaki (Terminalia chebula). Triphala is celebrated as the ultimate tridoshic balancer and gentle internal cleanser. It aids in deep detoxification (Ama pachana), promotes regular bowel motility without causing irritation, supports optimal gastrointestinal tract health, and enhances nutrient absorption during recovery.

  1. Dosage: 1 capsule twice daily, with plain water after meals.

5. Avipattikar Churna

A classic Ayurvedic herbal powder blend containing pungent and cooling herbs such as Trivrit (Operculina turpethum), Pippali (Piper longum), Maricha (Piper nigrum), Shunti (Zingiber officinale), and cloves. Avipattikar Churna is exceptionally effective in balancing gastric acidity, stimulating sluggish digestive fire (Agni), clearing obstruction in the gastrointestinal tract, and promoting mild, natural bowel cleansing to relieve abdominal bloating and discomfort.

Dosage: 1/2 teaspoon twice daily, with warm water after meals.

Conclusion

Encapsulating peritoneal sclerosis is an intricate and formidable medical challenge characterized by dense fibrocollagenous encasement of the bowel, leading to chronic obstruction and malnutrition. While conventional management relies heavily on nutritional rehabilitation, immunosuppression, and complex surgical adhesiolysis, integrative paradigms offer valuable supportive dimensions. By addressing the deep-seated root causes of Kapha-Vata imbalance, mitigating excessive fibrous proliferation through Lekhana actions, enhancing metabolic fire (Agni), and gently clearing channel obstructions (Srotoshodhana), specialized Ayurvedic protocols—featuring Mutrakrichantak Churna, Nephralka Capsules, Saral Ghan Vati, Triphala Capsules, and Avipattikar Churna—provide a comprehensive framework to support internal healing, improve gastrointestinal comfort, and enhance long-term vitality.

Rikobalin – Ingredients, Preparation, Indications & Dosages

Abstract

Rikobalin Capsule is a prescription medicine used primarily for the management of neuropathic pain. The formulation commonly available in India contains Pregabalin 75 mg and Methylcobalamin 750 mcg, combining a medicine that reduces abnormal nerve-pain signalling with an active form of vitamin B12 involved in normal nerve function and myelin formation. Neuropathic pain may occur in diabetes, post-herpetic neuralgia, nerve-root disorders and other conditions involving nerve injury. Rikobalin is particularly relevant when symptoms include burning, tingling, electric-shock-like pain, numbness or heightened sensitivity. Beyond conventional modern pharmacology, this paper explores an integrative Ayurvedic framework, conceptualising neuropathic disorders through the lens of Vata Vyadhi (hyperexcitation and nerve degeneration) and Majja Dhatu Kshaya (tissue depletion). By evaluating clinical efficacy across diabetic peripheral neuropathy, post-herpetic neuralgia, and spinal radiculopathy alongside holistic Ayurvedic protocols, this article offers a balanced perspective on managing complex nerve pain.

Buy Now Neurogenie Capsules

Buy Now Neurogenie Capsules

Introduction

Nerves continuously transmit sensory and motor information between different parts of the body and the brain. When these nerves become damaged or irritated, their normal signalling can become disturbed, producing symptoms such as burning, pins and needles, numbness, shooting pain or abnormal sensitivity. This type of pain is known as neuropathic pain. Diabetes is one of the important causes of peripheral neuropathy. Persistent metabolic disturbances associated with diabetes can affect peripheral nerves, particularly those supplying the feet and lower limbs. Some people experience painful burning or tingling, whereas others primarily develop numbness and loss of protective sensation. The latter can be particularly significant because an unnoticed injury may progress to a diabetic foot ulcer. The American Diabetes Association recommends regular assessment for diabetic peripheral neuropathy and treatment of neuropathic pain when present. Rikobalin Capsule combines pregabalin and methylcobalamin, providing two complementary approaches to nerve-related symptoms. Pregabalin acts on abnormal neuronal signalling, while methylcobalamin contributes to normal vitamin B12-dependent neurological functions.

What Is Rikobalin Capsule?

Rikobalin Capsule is a prescription combination used for neuropathic pain. The commonly listed composition is:

  • Pregabalin (75 mg)
  • Methylcobalamin (750 mcg)

The combination is particularly used when neuropathic pain is associated with conditions such as diabetic peripheral neuropathy, post-herpetic neuralgia and other nerve-related disorders. Unlike conventional painkillers that mainly target inflammatory or tissue-related pain, Rikobalin is directed toward abnormal nerve signalling. This makes its therapeutic role more relevant when pain is described as burning, shooting, tingling, electric-like or associated with altered sensation.

Understanding Neuropathic Pain

Neuropathic pain results from a lesion or disease affecting the somatosensory nervous system. It differs from ordinary nociceptive pain, which generally occurs when healthy pain receptors respond to tissue injury. Common features of neuropathic pain include:

  • Burning or hot sensation
  • Tingling or pins-and-needles sensation
  • Electric-shock-like pain
  • Shooting or stabbing pain
  • Numbness
  • Increased sensitivity to touch
  • Pain from normally non-painful stimuli
  • Discomfort that becomes more noticeable at night

In diabetic peripheral neuropathy, these symptoms commonly affect both feet or the lower limbs. However, diabetic neuropathy can also be asymptomatic, with loss of protective sensation occurring without obvious pain.

Composition of Rikobalin and Its Role

Pregabalin

Pregabalin is the primary analgesic component of Rikobalin. It binds with high affinity to the alpha-2-delta subunit of voltage-gated calcium channels in the central nervous system. Through this action, it reduces the release of certain neurotransmitters involved in abnormal pain signalling. This mechanism helps decrease excessive nerve excitability. Consequently, pregabalin can reduce symptoms such as burning pain, shooting pain and abnormal sensations associated with neuropathic disorders. Pregabalin is recognised in clinical guidelines as one of the pharmacological options for neuropathic pain. The 2026 ADA Standards of Care list gabapentinoids, including pregabalin, among the initial pharmacological options for painful diabetic peripheral neuropathy.

Methylcobalamin

Methylcobalamin is a metabolically active form of vitamin B12. Vitamin B12 is required for the development, myelination and normal function of the nervous system, as well as DNA synthesis and red blood cell formation. Myelin is the protective covering surrounding many nerve fibres and helps nerve impulses travel efficiently. Adequate vitamin B12 therefore has an important role in maintaining normal neurological function. The presence of methylcobalamin in Rikobalin complements pregabalin by providing nutritional support relevant to nerve structure and function, while pregabalin primarily addresses abnormal pain transmission.

How Rikobalin Works

The two components act through different but complementary mechanisms. Pregabalin reduces excessive nerve signalling by interacting with calcium-channel alpha-2-delta subunits. This decreases the release of neurotransmitters associated with pain transmission and helps calm hyperexcitable neural pathways. Methylcobalamin supports vitamin B12-dependent neurological processes. It contributes to normal myelin formation and maintenance, which are important for efficient nerve conduction. Together, these actions can help address both the symptomatic component of neuropathic pain and nutritional support of normal nerve function.

Clinical Indications and Therapeutic Efficacy

Rikobalin is indicated across a wide spectrum of neuropathic conditions, providing substantial symptomatic relief and functional restoration:

Diabetic Peripheral Neuropathy (DPN)

Long-term hyperglycemia causes microvascular damage to the vasa nervorum, leading to ischemia and chronic metabolic toxicity in peripheral nerves. Rikobalin reduces the distal symmetric burning pain, numbness, and nocturnal tingling typical of DPN.

Post-Herpetic Neuralgia (PHN)

Following a varicella-zoster (shingles) reactivation, localised nerve damage can cause persistent, agonising pain. Rikobalin calms localised cutaneous hypersensitivity and deep aching sensations.

Spinal Radiculopathy and Sciatica

Mechanical compression or inflammation of spinal nerve roots caused by herniated discs or lumbar stenosis triggers radiating peripheral pain. Rikobalin lowers the hypersensitivity of compressed root fibres.

Fibromyalgia

Characterised by widespread musculoskeletal pain, sleep disturbances, and altered central pain processing, fibromyalgia benefits from the central nervous system calcium-channel modulating effects of Rikobalin’s Pregabalin component.

Trigeminal Neuralgia

Used as an adjunctive or second-line strategy when conventional anti-epileptic therapies (such as carbamazepine) produce intolerable side effects or sub-optimal pain control.

Role in Diabetic Peripheral Neuropathy

Diabetic peripheral neuropathy is one of the most common forms of peripheral neuropathy. It frequently affects the feet first because the longest nerves supplying the lower limbs are particularly vulnerable. High blood glucose over time can contribute to metabolic and vascular changes that adversely affect peripheral nerves. Symptoms may include burning feet, tingling, numbness, sharp pain and increased sensitivity. Rikobalin may be used when painful diabetic neuropathy is present. Pregabalin helps reduce abnormal pain transmission, while methylcobalamin provides vitamin B12 support relevant to nerve function. The ADA specifically recognises pregabalin as a treatment option for painful diabetic peripheral neuropathy. An important distinction is that neuropathic pain and loss of sensation are different manifestations of diabetic neuropathy. Reducing pain does not necessarily mean that the underlying nerve damage has been reversed. Therefore, sensory assessment and regular foot examination remain important components of diabetic care.

Symptoms That May Respond to Rikobalin

Rikobalin is most relevant when diabetic or other nerve-related pain presents with characteristic neuropathic symptoms, including:

  • Burning sensation: A persistent burning feeling in the feet is a common manifestation of peripheral neuropathy.
  • Tingling and pins-and-needles: Abnormal sensory signals may create continuous or intermittent tingling.
  • Shooting pain: Irritated nerves can produce sudden, sharp or electric-like pain.
  • Numbness with discomfort: Some individuals experience both reduced sensation and episodes of pain.
  • Night-time nerve pain: Neuropathic symptoms may become particularly troublesome at night and interfere with sleep.

The response varies according to the underlying cause, severity and individual characteristics.

Ayurvedic Insight

In Classical Ayurveda, disease is understood as an imbalance among the three primary functional forces (Doshas): Vata, Pitta, and Kapha. Neuropathic disorders map directly to disturbances within the domain of Vata Dosha, specifically those conditions categorised as Vata Vyadhi.

Pathophysiology in Ayurveda

Vata Aggravation

Vata possesses qualities (Gunas) that are dry (Ruksha), light (Laghu), cold (Sheeta), and mobile (Chala). Factors such as metabolic derangements (Diabetes), poor nutrition, chronic stress, or structural degeneration aggravate Vata. This leads to Suptata (numbness), Toda (pricking/stabbing pain), and Kampa (tremors or instability).

Majja Dhatu Kshaya (Depletion of Bone Marrow and Nervous Tissue)

The nervous system correlates closely with Majja Dhatu (bone marrow and neural tissue). Chronic high blood sugar or nerve injury leads to Kshaya (depletion or atrophy) of Majja Dhatu (Bone marrow tissue), stripping nerves of their protective nourishers (akin to demyelination).

Avarana (Covering)

In conditions like diabetic neuropathy, accumulated metabolic toxins (Ama) obstruct the movement of Vata (Avarana), causing localised stagnation, localised Daha (burning sensation, often involving Pitta), and dysesthesias.

Herbal Remedies by Planet Ayurveda for an Alternative to Rikobalin

Planet Ayurveda offers a wide range of Ayurvedic medicines and herbal formulations made with carefully selected herbs and traditional ingredients. These formulations are designed to support the body’s natural balance and promote overall well-being. The medicines focus on addressing the underlying imbalance associated with different health concerns. Herbal ingredients are selected according to their traditional Ayurvedic properties and therapeutic actions. Different formulations are available to support digestion, metabolism, immunity, joints, liver health, skin, and other body systems. The products are prepared with attention to quality, purity, and traditional Ayurvedic principles. Planet Ayurveda medicines provide convenient herbal options for incorporating Ayurveda into daily health care. The formulations are developed to support healthy physiological functions and maintain Dosha balance. With a broad range of herbal products, Planet Ayurveda brings traditional Ayurvedic wellness into modern routines. Here, we will discuss the Ayurvedic alternative to Rikobalin. Let’s start!

  1. Neurogenie Capsule

Product Description

Neurogenie Capsule

Neurogenie Capsule of Planet Ayurveda, containing Brahmi (Bacopa monnieri) and Ashwagandha (Withania somnifera), offers a herbal approach to supporting nerve health in neuropathic pain. Brahmi is traditionally valued for supporting neuronal function, memory and mental calmness, while its bioactive constituents such as bacosides provide antioxidant support to nerve cells. Ashwagandha contains withanolides that may help maintain a healthy inflammatory response and support nerve resilience. Together, these herbs may help reduce oxidative stress, promote nervous-system balance and support healthy nerve signalling. Their calming and restorative properties may also be beneficial when burning, tingling, discomfort or sleep disturbance accompany neuropathic pain. Thus, Neurogenie Capsule can be considered a plant-based option for comprehensive nerve nourishment and long-term neurological support.

Dosage: 1 capsule twice daily after a meal with plain water.

Conclusion

Rikobalin Capsule combines pregabalin 75 mg with methylcobalamin 750 mcg, addressing neuropathic symptoms through two complementary mechanisms. Pregabalin reduces excessive pain signalling through its action on neuronal calcium-channel alpha-2-delta subunits, while methylcobalamin provides vitamin B12 activity important for normal nerve function and myelination. Its role is particularly relevant in painful peripheral neuropathy, including diabetic neuropathic pain. From an Ayurvedic perspective, nerve-related symptoms can be viewed through the involvement of Vata, Majja Dhatu (Bone marrow tissue), Agni (Digestive fire) and broader metabolic imbalance. A comprehensive approach combining appropriate medical treatment, metabolic control, neurological assessment and consistent foot care is central to maintaining nerve and foot health

Herbal Remedies of Eye Ulcer/ Corneal Ulcer – Causes, Symptoms, Diagnosis & Treatment

Abstract

Corneal ulceration (eye ulcer) is an ophthalmic emergency involving epithelial layer disruption and progressive destruction of the underlying corneal stroma.  It is an open sore or defect on the cornea, the transparent front surface of the eye. It is usually associated with infection and inflammation, although trauma, contact-lens misuse, severe dry eye, eyelid disorders, and nutritional deficiencies can also contribute. A corneal ulcer may progress rapidly and cause corneal scarring, reduced vision, corneal perforation, or permanent loss of sight if treatment is delayed. The condition requires urgent examination by an ophthalmologist. Diagnosis is based on clinical history, visual-acuity testing, slit-lamp examination, and fluorescein staining. Corneal scraping and laboratory testing may be required to identify the causative organism. Modern treatment centres on intensive topical antimicrobials and surgical repair, while Ayurveda views it as Kshata Shukra or Vrana Shukra—a severe Vata-Pitta and Rakta imbalance—offering complementary cooling and tissue-healing modalities.

Eye Ulcer/ Corneal Ulcer

Introduction

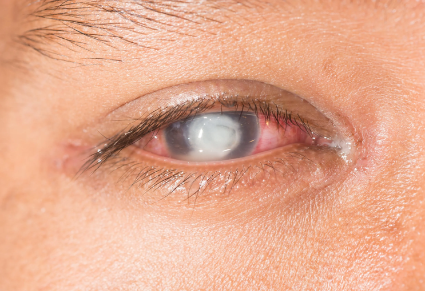
The cornea is the clear, dome-shaped tissue covering the front of the eye. It allows light to enter the eye and plays an important role in focusing images onto the retina. The cornea contains several layers, including the epithelium, Bowman’s layer, stroma, Descemet’s membrane, and endothelium. The outer epithelial layer acts as a protective barrier against microorganisms, dust, chemicals, and physical injury. When this protective layer is damaged, microorganisms can enter the corneal tissue and produce inflammation. The resulting open lesion is called a corneal ulcer or ulcerative keratitis. As a primary cause of preventable blindness worldwide, corneal ulceration progresses rapidly. A delay of 24 to 48 hours can allow destructive enzymes to melt stromal collagen, leaving behind permanent scars or resulting in structural collapse of the eyeball. It may appear as a white, grey, or yellowish spot on the cornea and is often accompanied by eye pain, redness, watering, photophobia, and blurred vision. A corneal ulcer is considered an ophthalmic emergency because infection can spread into the deeper corneal layers within a short period. Severe disease can lead to corneal thinning, perforation, infection inside the eye, and permanent visual impairment. Early diagnosis and appropriate treatment are essential for protecting vision.

Causes

Bacterial Infection

Bacteria are a common cause of corneal ulcers. Organisms such as Staphylococcus, Streptococcus, and Pseudomonas may enter the cornea through a damaged epithelial surface. Bacterial ulcers may progress quickly, particularly when the infection is caused by aggressive organisms. Contact-lens users are at increased risk when lenses are worn overnight, cleaned improperly, exposed to tap water, or used beyond the recommended replacement period. Poor hygiene can allow bacteria to multiply on the lens or lens case.

Fungal Infection

Fungal corneal ulcers may develop after injury from soil, leaves, wood, agricultural material, or other plant matter. Common fungal organisms include Fusarium, Aspergillus, and Candida species. Fungal ulcers may progress slowly and can be difficult to distinguish from other types of corneal infection. They may produce irregular infiltrates, satellite lesions, or deep stromal involvement.

Viral Infection

Herpes simplex virus can affect the cornea and produce epithelial or stromal keratitis. A typical herpes-related lesion is a branching ulcer called a dendritic ulcer. Recurrent infection may reduce corneal sensation and increase the risk of repeated injury and scarring. Herpes zoster, the virus responsible for shingles, may also affect the eye and cause corneal inflammation or ulceration.

Acanthamoeba Infection

Acanthamoeba is a microscopic organism found in soil and water. It can cause a serious corneal infection, especially in contact-lens users who swim, shower, or wash lenses with contaminated water. Acanthamoeba keratitis may cause intense eye pain, sometimes more severe than the visible eye findings suggest. Diagnosis may be delayed because the condition can resemble bacterial, fungal, or viral keratitis.

Trauma and Foreign Bodies

A scratch caused by a fingernail, plant, dust particle, metal fragment, or other foreign body can damage the corneal epithelium. If bacteria or fungi enter the injured area, the abrasion may develop into an ulcer. Chemical injuries can also damage the cornea and create an opportunity for secondary infection.

Dry Eye and Eyelid Disorders

Severe dry eye reduces the protective tear film that keeps the cornea moist and provides antimicrobial protection. Incomplete eyelid closure, inward-turning eyelashes, chronic eyelid inflammation, and eyelid abnormalities can also cause repeated surface damage.

Other Risk Factors

Other conditions associated with corneal-ulcer development include:

  • Diabetes mellitus
  • Vitamin A deficiency
  • Poor nutritional status
  • Reduced immunity
  • Previous eye surgery
  • Chronic ocular-surface disease
  • Long-term or unsupervised steroid eye-drop use
  • Poor contact-lens hygiene
  • Reduced corneal sensation
  • Delayed treatment of eye injury

Pathophysiology

The pathology begins when a breach in the epithelium allows pathogens to attach to the stroma. Microorganisms release exotoxins and proteolytic enzymes (collagenases and elastases) that break down the organised collagen matrix. In response, the host immune system sends polymorphonuclear neutrophils (PMNs) from limbal blood vessels into the avascular stroma. While trying to clear the infection, these neutrophils release reactive oxygen species and matrix metalloproteinases (MMPs). This intense immune reaction causes collateral tissue destruction, known as “stromal melting.” If unchecked, necrosis deepens toward Descemet’s membrane, creating a bulging descemetocele that can rupture into a full corneal perforation.

Signs and Symptoms

The symptoms of a corneal ulcer depend on its cause, depth, location, and rate of progression. Common symptoms include:

  • Severe Pain & Foreign Body Sensation: Driven by dense sensory nerve endings in the cornea.
  • Marked Redness & Ciliary Flush: Engorged blood vessels encircling the iris junction.
  • Intense Photophobia & Epiphora: Hypersensitivity to light accompanied by excessive tearing or mucopurulent discharge.
  • Reduced Visual Acuity: Blurring caused by corneal oedema or opaque infiltrates in the visual axis.
  • Corneal Infiltrate: A visible grayish-white focal opacity on the clear corneal surface.
  • Hypopyon: A layer of pus (inflammatory white blood cells) settling at the bottom of the anterior chamber.

Diagnosis

Medical History

The ophthalmologist will ask about the duration of symptoms, contact-lens use, recent trauma, exposure to soil or plant material, previous herpes infection, eye surgery, medication use, and underlying diseases.

Visual Acuity Testing

Visual acuity is measured in both eyes. This establishes the degree of visual disturbance and provides a baseline for monitoring improvement or deterioration.

Slit-Lamp Examination

A slit lamp provides a magnified view of the cornea, conjunctiva, anterior chamber, and eyelids. It helps determine the size, depth, location, and appearance of the ulcer.

Fluorescein Staining

Fluorescein is a special dye that highlights defects in the corneal epithelium. Under blue light, the damaged area appears green, helping the doctor identify the ulcer and assess its margins.

Corneal Scraping

Corneal scraping may be performed when the ulcer is large, central, deep, atypical, recurrent, or unresponsive to initial treatment. The sample may be examined under a microscope and sent for culture to identify bacteria, fungi, or other organisms.

Additional Evaluation

The doctor may assess corneal sensation, tear production, eyelid closure, intraocular inflammation, and the presence of diabetes or immune-system disorders. Additional testing depends on the suspected cause.

Modern Treatment

The choice of medicine depends on the suspected organism, severity, location, and depth of the ulcer. The general treatment protocol is as follows:

  • Topical Antimicrobials: Frequent antibiotic drops; antifungals or antivirals when indicated.
  • Cycloplegics: Atropine or cyclopentolate relieve pain and prevent adhesions.
  • Surgery: AMT supports healing, CXL strengthens and sterilises the cornea, and therapeutic keratoplasty is used for severe melting or perforation

Ayurveda Insight

In Ayurvedic classics (Shalakya Tantra), corneal disorders affect the Krishna Mandala (dark circular region of the eye). A corneal ulcer corresponds to Kshata Shukra (ulceration due to injury) or Vrana Shukra (ulcerative corneal opacity). The pathology stems from an acute imbalance of Vata (causing sharp pain, dryness, and tissue breakdown) and Pitta (driving inflammation, burning, redness, and suppuration), which vitiates Rakta (blood) and Mamsa (muscle) tissues. Accumulating metabolic waste (Ama) blocks the ocular channels (Srotas), trapping heat and toxins within the eye.
Complementary Ayurvedic care focuses on soothing heat, balancing Pitta, and encouraging tissue regeneration (Vrana Ropana):

  • Seka & Aschyotana: Washing the closed eye or applying drops made from cooling herbal decoctions such as Triphala Kwatha or Yashtimadhu (Liquorice) to calm acute irritation.
  • Tarpana: During the post-acute healing phase, pooling warm medicated ghee (Maha Triphala Ghrita) over the eye nourishes the stroma and aids tissue repair.

Herbal Remedies for Eye Ulcer by Planet Ayurveda

Planet Ayurveda offers a wide range of Ayurvedic medicines and 100% herbal supplements. The products are prepared using carefully selected herbs and traditional Ayurvedic formulations. Each medicine is developed to support specific health needs naturally. The formulations focus on promoting balance, strength, and overall wellness. Planet Ayurveda combines classical Ayurvedic knowledge with quality manufacturing practices. The product range includes herbal capsules, tablets, powders, syrups, oils, and other preparations. These medicines are made to support healthy digestion, immunity, metabolism, and general well-being. Planet Ayurveda aims to make reliable Ayurvedic healthcare accessible and affordable worldwide. In this article, we will discuss some Ayurveda formulations by Planet Ayurveda for the management of Eye Ulcers. Let’s Start!

  1. Angel Eye Vitale
  2. Bilberry Capsule
  3. Amalaki Rasayan
  4. Mahatriphala Ghrit
  5. Jasnoor Eye Drops

Care Pack of Eye Ulcer

Buy Now Care Pack of Eye Ulcer

Buy Now Care Pack of Eye Ulcer

Product Description

Angel Eye Vitale

Angel Eye Vitale contains Amla (Emblica officinalis), Gotukola (Centella asiatica), and Bhringraj (Eclipta alba), which are traditionally used to support eye health. Amla provides antioxidant support and helps protect ocular tissues from oxidative stress. Gotukola supports collagen formation and may promote healthy tissue repair. Bhringraj is traditionally valued for maintaining clear vision and nourishing the eyes. Together, these herbs may support corneal strength, tissue nourishment, and comfort. Their combined properties may also help maintain healthy inflammatory balance and support recovery in eye-related conditions. 

Dosage: 1 Capsule twice daily after a meal with plain water.

Bilberry Capsule

Bilberry Capsule contains Vaccinium myrtillus, a rich source of anthocyanins and other antioxidant compounds that support healthy ocular tissues. These compounds help protect eye cells from oxidative stress and support normal microcirculation around the eyes. Bilberry may also support retinal and vascular health, which contributes to overall visual function. Its antioxidant properties can help maintain healthy inflammatory balance and protect delicate ocular structures. By supporting tissue nourishment and circulation, it may be useful as part of general eye-health care.

Dosage: 1 Capsule twice daily after a meal with plain water.

Amalaki Rasayan

Amalaki Rasayan contains Amla (Emblica officinalis), which is traditionally valued for its cooling, rejuvenating, and antioxidant properties. Its rich vitamin C and polyphenol content may help protect ocular tissues from oxidative stress. Amla supports healthy collagen formation, an important component of the corneal structure. It may also promote tissue nourishment and maintain the natural moisture balance of the eyes. Its Pitta-pacifying properties are traditionally associated with reducing burning, irritation, and heat-related eye discomfort. By supporting ocular strength and healthy tissue repair, Amalaki Rasayan may be beneficial as part of supportive care for eye ulcers.

Dosage: 1 Capsule twice daily after a meal with plain water.

Mahatriphala Ghrit

Mahatriphala Ghrit contains Triphala (Emblica officinalis, Terminalia chebula, Terminalia bellirica), Bhringraj (Eclipta alba), Vasa (Adhatoda vasica), Shatavari (Asparagus racemosus), Guduchi (Tinospora cordifolia), Amla (Emblica officinalis), Yashtimadhu (Glycyrrhiza glabra), Nilotpala (Nymphaea stellata),  Pippali (Piper longum), and other supportive herbs processed in ghrita. Triphala and Amla provide antioxidant support, while Bhringraj, Vasa, and Guduchi help maintain healthy inflammatory balance. Ghrita acts as a nourishing base and is traditionally considered beneficial for Vata-Pitta-related eye disorders. Yashtimadhu and Nilotpala may help soothe irritation and support ocular comfort. Together, these ingredients may promote eye-tissue nourishment, support corneal strength, and assist the natural healing environment in eye-related conditions.

Dosage: 1 tsp twice daily after a meal with warm water.

Jasnoor Eye Drops

Jasnoor Eye Drops contain Neem (Azadirachta indica), Shobhanjana (Moringa oleifera), Bhringraja (Eclipta alba), Punarnava (Boerhavia diffusa), Nirgundi (Vitex negundo), and Tulsi (Ocimum tenuiflorum), along with other herbal ingredients. Neem provides cleansing and antimicrobial support for maintaining a healthy ocular surface. Shobhanjana is traditionally valued for its nourishing and antioxidant properties. Bhringraja supports eye strength and tissue nourishment. Punarnava helps maintain healthy fluid balance and may support comfort around the eyes. Nirgundi and Tulsi provide soothing and anti-inflammatory support for irritated ocular tissues. Together, these herbs may help maintain corneal moisture, cleanliness, and a healthy healing environment. The formulation may therefore support comfort and tissue recovery in eye-related conditions such as corneal ulcers.

Dosage: Use 1–2 drops in each eye, three to four times a day, or follow your Ayurvedic doctor’s instructions.

Prevention

Preventive measures include:

  • Washing hands before touching the eyes or contact lenses
  • Following proper contact-lens cleaning instructions
  • Replacing lenses and lens cases as recommended
  • Avoiding overnight lens wear unless specifically advised
  • Never washing lenses with tap water
  • Avoiding swimming or showering while wearing lenses
  • Using protective eyewear during hazardous work
  • Seeking immediate care after a corneal injury
  • Avoiding unsupervised steroid eye drops
  • Managing diabetes and chronic dry eye
  • Treating eyelid inflammation and abnormal eyelashes
  • Avoiding non-sterile substances in the eyes

Conclusion

A corneal ulcer is a potentially vision-threatening condition involving a defect in the cornea and associated inflammation. Bacterial, fungal, viral, and parasitic infections are important causes, while trauma, contact-lens misuse, dry eye, eyelid disorders, and systemic disease increase susceptibility. Pain, redness, watering, photophobia, blurred vision, and a white corneal spot are important warning signs. Diagnosis requires urgent ophthalmic examination, slit-lamp evaluation, and fluorescein staining. Corneal scraping and laboratory testing may be needed to identify the causative organism. Modern treatment includes intensive antimicrobial or antiviral therapy, management of contributing eye-surface disorders, close monitoring, and surgery in advanced cases. Ayurveda offers a traditional perspective based on Dosha balance, Rakta Dhatu (Blood tissue), and Netra (Eye) health. Early diagnosis and appropriate care are essential to prevent corneal scarring, perforation, and permanent loss of vision.

Estrogen Detox Can Prevent Breast Cancer

Abstract

Estrogen is an indispensable hormone responsible for regulating the female reproductive system, bone density, and cardiovascular health. However, when the body’s natural estrogen pathways become overloaded or impaired, an imbalance known as estrogen dominance can occur. Chronic exposure to elevated levels of estrogen—specifically toxic metabolites produced during improper breakdown—is a major contributor to the development and progression of hormone-receptor-positive breast cancers. Estrogen detoxification refers to the biological processes by which the liver, gastrointestinal tract, and cellular pathways metabolise and eliminate surplus estrogen. Enhancing these biochemical clearance mechanisms through targeted nutrition, lifestyle interventions, and traditional medical systems like Ayurveda reduces cellular damage, controls tissue proliferation, and significantly lowers breast cancer risk.

Prevent Breast Cancer

Introduction

Breast cancer remains one of the most common malignancies affecting women worldwide. While genetic factors such as BRCA (BReast CAncer gene) mutations play a critical role, environmental exposures, lifestyle habits, and endocrine disruptors account for a substantial percentage of cases. Among the key hormonal drivers of breast tissue hyperplasia is human estrogen. In healthy physiological conditions, estrogen circulates, performs its biological signals, and is promptly broken down by hepatic enzymes before being excreted through urine and stool. Modern lifestyles—marked by chronic stress, nutrient-poor diets, alcohol consumption, high body fat composition, and constant contact with synthetic xenoestrogens—frequently overload these clearance pathways. When the rate of estrogen production and intake exceeds the body’s capacity to detoxify it, circulating levels spike, leading to tissue hyper-responsiveness. Under these conditions, specific downstream metabolites interact directly with DNA in breast cells, creating mutations that initiate oncogenesis. Understanding and supporting the biochemical and physiological pathways of estrogen detoxification is therefore a cornerstone of primary breast cancer prevention.

Understanding Estrogen and Its Role in Breast Health

Estrogen is a group of steroid hormones, including estradiol, estrone, and estriol. Estradiol is the predominant estrogen during the reproductive years. It is produced mainly by the ovaries before menopause, while after menopause, estrogen production occurs primarily through the conversion of androgens in peripheral tissues, including adipose tissue. Breast tissue contains estrogen receptors, particularly estrogen receptor alpha (ERα), which allow estrogen to influence cellular activity. When estrogen binds to these receptors, it can activate signals that promote cell growth and proliferation. This is a normal physiological process, but persistent stimulation can contribute to the development and progression of hormone-sensitive breast cancer. Estrogen exposure is influenced by several factors, including the age at which menstruation begins, age at menopause, pregnancy history, hormone replacement therapy, and body composition. The cumulative duration of exposure matters because breast cells may undergo repeated cycles of growth and division over many years. Research also indicates that estrogen may contribute to carcinogenesis through mechanisms beyond receptor stimulation. Certain estrogen metabolites can undergo oxidation and produce reactive intermediates capable of damaging DNA. This provides a biological rationale for studying estrogen metabolism in relation to breast cancer risk.

What Is Estrogen Detoxification?

Estrogen detoxification is the physiological process through which the body transforms and eliminates estrogen and its metabolites. It is not a single reaction but a series of metabolic steps involving the liver, blood, intestines, and kidneys. The process can be understood in three broad stages:

  • Metabolism: Estrogen is chemically modified in the liver through enzyme-mediated reactions.
  • Conjugation: The metabolites are attached to molecules such as glucuronic acid or sulfate, which generally makes them more water-soluble.
  • Elimination: The modified compounds leave the body through urine or bile. Estrogen excreted in bile may reach the intestines, where bacterial enzymes can alter some conjugated metabolites and permit reabsorption.

This process is regulated by enzymes and depends on overall liver function, intestinal activity, and hormonal physiology. A healthy body does not need a special detoxification program to perform these functions. The scientific question is whether particular dietary or lifestyle interventions can meaningfully alter estrogen exposure or reduce cancer risk

How Estrogen Metabolism Relates to Breast Cancer

Estrogen may influence breast cancer development through two major pathways.

Estrogen receptor signalling

Estrogen binds to receptors in breast cells and activates gene expression involved in cellular growth. In hormone receptor-positive breast cancer, these signals can support tumour development or progression.

Oxidative and DNA-damaging pathways

Estrogen metabolism produces compounds that can undergo further oxidation. Some reactive metabolites may interact with DNA and form damage, while oxidative stress may affect cellular repair mechanisms. These processes are biologically plausible contributors to carcinogenesis, although the relationship between individual estrogen metabolites and a person’s actual breast cancer risk is complex.

How Healthy Estrogen Metabolism Supports Breast Wellness

Maintaining Hormonal Balance

The body requires estrogen for normal breast development and reproductive health. Balanced estrogen metabolism helps maintain appropriate hormone levels according to age and physiological needs. Hormonal balance is influenced by the interaction of estrogen with other hormones, including progesterone. Supporting overall endocrine health through nutritious food, adequate sleep, and regular physical activity can contribute to general well-being.

Supporting Liver Function

The liver is an important organ for hormone metabolism. Healthy liver function supports the processing of estrogen and many other substances in the body. A diet rich in vegetables, whole grains, fruits, and adequate protein provides nutrients required for normal liver function. Limiting excessive alcohol intake and maintaining a healthy body weight also supports liver wellness.

Promoting Healthy Digestion

Estrogen metabolites eliminated through bile pass into the digestive tract. Normal intestinal function contributes to the body’s elimination processes. Dietary fiber from vegetables, fruits, legumes, and whole grains supports bowel regularity and healthy digestion. Adequate water intake and regular physical activity further support digestive health.

Supporting Healthy Body Composition

Adipose tissue participates in estrogen production through the conversion of certain hormones into estrogen. Maintaining a healthy body composition is therefore relevant to hormonal wellness, particularly after menopause.

The Role of Body Fat and Insulin Resistance

After menopause, adipose tissue becomes an important source of estrogen production. Fat tissue contains aromatase, an enzyme that converts certain androgens into estrogens. Increased body fat may therefore increase estrogen exposure in some postmenopausal women. Obesity is also associated with insulin resistance, chronic low-grade inflammation, and altered growth-factor signalling. These changes may create a biological environment that supports abnormal cell growth. Gradual weight management may help reduce several breast cancer risk factors simultaneously. It should be approached through sustainable nutrition, physical activity, sleep, and metabolic care rather than extreme dieting.

Liver Health and Estrogen Processing

The liver is responsible for transforming many hormones, medicines, and metabolic compounds. Conditions such as fatty liver disease, excessive alcohol intake, and certain medication-related injuries may impair normal liver function. Supporting liver health includes:

  • Maintaining a healthy body weight
  • Eating a balanced diet
  • Limiting alcohol
  • Avoiding unnecessary supplements
  • Managing diabetes and abnormal cholesterol
  • Following medical advice for liver disease
  • Staying physically active

A liver-supportive lifestyle may contribute to normal hormone metabolism, but it does not guarantee the prevention of breast cancer.

Lifestyle Measures That May Reduce Breast Cancer Risk

Regular Physical Activity

Physical activity is associated with a lower risk of breast cancer. Exercise may help through several mechanisms, including improved insulin sensitivity, reduced body fat, lower inflammation, and changes in hormone availability. A practical routine may include brisk walking, strength training, cycling, swimming, or other activities performed consistently according to individual ability.

Limiting Alcohol

Alcohol consumption is a recognised breast cancer risk factor. It may influence estrogen levels and other biological pathways involved in carcinogenesis. Reducing alcohol intake or avoiding it altogether may lower risk.

Maintaining a Healthy Weight

Healthy body composition is particularly relevant after menopause, when adipose tissue contributes more substantially to estrogen production. Weight management should focus on gradual, sustainable changes rather than rapid weight loss.

Breastfeeding When Possible

Breastfeeding is associated with a reduction in breast cancer risk. The protective relationship may involve changes in breast tissue differentiation, hormonal exposure, and the number of menstrual cycles over a lifetime.

Avoiding Unnecessary Hormonal Exposure

Menopausal hormone therapy may provide important symptom relief for some individuals, but its benefits and risks vary according to the type of therapy, duration, age, and medical history.

Ayurvedic Insight

Ayurveda provides a traditional framework for understanding metabolism, tissue nourishment, elimination, and physiological equilibrium. Classical Ayurvedic texts do not describe estrogen using modern chemical terminology, but some traditional concepts may be used to discuss reproductive and metabolic health.

The Role of Agni and Ama

In Ayurveda, efficient tissue health (Dhatu Agni) relies entirely on strong central digestion (Jatharagni). When Agni (Digestive Fire) is weak, food and metabolic byproducts are incompletely processed, leading to the formation of Ama—a sticky, toxic, morbid substance that circulates throughout the bodily channels (Srotas).
In the context of modern pathology, toxic estrogen metabolites (such as 4-hydroxyestrone and quinones) represent a molecular form of Ama circulating within Rasa (plasma) and Rakta (blood) dhatus. Accumulations of Ama block Artava Vaha Srotas (the channels regulating female reproductive health and hormonal tissue), establishing a breeding ground for tissue hyper-growth, cysts, and tumours (Granthi and Arbuda).

Dosha Imbalances in Estrogen Dominance

Estrogen dominance typically exhibits a dual imbalance of Kapha and Pitta:

  • Excess Kapha manifests as cellular proliferation, tissue congestion, fluid retention, weight gain, and slow, sluggish elimination. Kapha’s heavy, slow qualities impair the natural clearance pathways.
  • Excess Pitta reflects inflammatory conditions, heat, liver congestion, and altered blood metabolism. Since the liver (Yakrit) is a primary seat of Pitta, a congested, overheated Pitta state impairs the liver’s ability to process blood-borne toxins, directly hindering modern Phase I and Phase II clearance.

Herbal Remedies  for Estrogen Detox by Planet Ayurveda

Planet Ayurveda offers a wide range of herbal medicines and wellness products prepared according to traditional Ayurvedic principles. The formulations contain carefully selected herbs and natural ingredients to support different aspects of health and well-being. The product range includes medicines for digestion, immunity, respiratory health, joint care, liver support, skin health, and general vitality. Each formulation is developed with attention to ingredient quality, traditional knowledge, and everyday healthcare needs. Planet Ayurveda focuses on providing herbal solutions that are convenient, affordable, and easy to include in a wellness routine. The medicines are intended to support the body’s natural functions and promote balanced health. With its commitment to authentic Ayurvedic care, Planet Ayurveda aims to bring herbal healthcare closer to people worldwide. Here, we will discuss some formulations for estrogen detox that will further help in preventing breast cancer. Let’s start!

  1. Yakrit Plihantak Churna
  2. Female Health Support Capsules
  3. Kumaryasav

Herbal Remedies  for Estrogen Detox

Buy Now Herbal Remedies  for Estrogen Detox

Buy Now Herbal Remedies  for Estrogen Detox

Product Description

Yakrit Plihantak Churna

Yakrit Plihantak Churna contains Bhumyamalaki (Phyllanthus niruri), Kalmegh (Andrographis paniculata), Bhringraj (Eclipta alba), Sharpunkha (Tephrosia purpurea), Kaasni (Cichorium intybus), Katuki (Picrorhiza kurroa), Makoy (Solanum indicum), and Punarnava (Boerhavia diffusa). These herbs are traditionally used to support Yakrit (liver function) and healthy metabolic activity. The liver plays an important role in the transformation and elimination of estrogen metabolites. Bhumyamalaki, Kalmegh, and Katuki provide bitter herbal support for digestion and hepatobiliary function. Bhringraj, Makoy, and Punarnava are traditionally valued for their antioxidant and liver-supportive properties. Kaasni and Sharpunkha further support digestive balance and normal metabolic processes. Together, these herbs may help maintain efficient liver function and support the body’s natural hormonal balance.

Dosage: 1 tsp twice daily with warm water after a meal.

Female Health Support Capsules

Female Health Support Capsules contain Ashoka (Saraca indica), Lodhra (Symplocos racemosa), and Shatavari (Asparagus racemosus), traditionally used to support female reproductive health. Ashoka and Lodhra help maintain healthy menstrual function and support the normal condition of uterine tissues. Shatavari provides nourishment for female physiology and contains steroidal saponins involved in reproductive wellness. These herbs support balanced hormonal activity and healthy reproductive-tissue function. Their antioxidant properties help protect cells against oxidative stress and free-radical damage. Healthy menstrual function and tissue nourishment are important aspects of maintaining estrogen balance. The formulation supports the body’s overall hormonal wellness, including the normal processing of estrogen through the liver and other elimination pathways. By supporting reproductive health and cellular protection, these herbs contribute to a holistic approach to breast health.

Dosage: 1 capsule twice daily with plain water after a meal.

Kumaryasav

Kumaryasava contains Kumari (Aloe barbadensis), Sonth (Zingiber officinale), Pippali (Piper longum), Kali Maricha (Piper nigrum), and Lोह Bhasma (iron calx), along with other traditional ingredients. Kumari supports liver and digestive function, which are important for the normal metabolism and elimination of estrogen metabolites. Sonth, Pippali, and Kali Maricha support Agni (digestive fire) and improve the processing of nutrients and herbal constituents. These herbs also promote healthy gastrointestinal movement, supporting the elimination of waste through the bowel. Aloe vera and the pungent herbs provide antioxidant support that helps protect cells from oxidative stress. In Ayurvedic terms, Kumaryasava supports Yakrit (liver), Agni (metabolism), and Malashodhana (proper bowel elimination). This supports the body’s natural hormonal balance and the normal processing of estrogen.

Dosage: 10 ml twice daily with plain water after a meal.

Conclusion

Estrogen metabolism is an important biological process that may influence breast cancer risk, particularly in hormone-sensitive breast cancers. The liver modifies estrogen, while the intestines and kidneys participate in its elimination. Differences in estrogen metabolites may be associated with cancer risk, but no detoxification diet, herb, or supplement has been established as a reliable method of preventing breast cancer. A balanced diet, regular exercise, healthy body composition, limited alcohol intake, adequate sleep, and appropriate medical care can support overall hormonal and metabolic health. Ayurveda offers traditional concepts such as Agni (metabolic fire), Artava (reproductive function), and Dosha balance to understand these processes holistically.

Estrogen Detox and Herbs for Estrogen Detoxification

Abstract

Estrogen is an important reproductive hormone that plays a major role in the menstrual cycle, fertility, bone health, and many other functions in the body. After estrogen has completed its function, estrogen is metabolized mainly in the liver and subsequently eliminated through bile and urine . The term “estrogen detox” is commonly used to describe practices that support this natural process. It does not mean that estrogen is a harmful substance that must be completely removed from the body. Ayurveda also emphasizes healthy Agni (digestion and metabolism), proper elimination of Mala (waste products), and maintaining the balance of Doshas and Dhatus. Certain herbs traditionally used in Ayurveda may support digestion, liver function, metabolism, and elimination. This article explains estrogen metabolism in simple terms and discusses the possible role of selected Ayurvedic herbs. 

Estrogen Detoxification

What Does Estrogen Detox Mean?

In simple words, estrogen detox means supporting the body’s natural way of handling estrogen. The process can be understood in three basic steps:
Estrogen production → Liver processing → Elimination through urine and stool
The liver changes estrogen into different forms so that it can be eliminated more easily. Some of these compounds are removed through urine, while others pass into bile and reach the intestine.The health of the liver, digestive system, gut microbiome, and bowel movements can therefore influence how efficiently these compounds are eliminated.

How Does the Body Process Estrogen?

The liver is one of the main organs involved in estrogen metabolism. It processes estrogen through several biochemical reactions.

Phase I

In the first stage, enzymes belonging mainly to the cytochrome P450 family  modify estrogen and convert it into different metabolites

Phase II

These metabolites are then combined with other substances through a process called conjugation. This makes them generally easier for the body to transport and eliminate.

Elimination

The processed estrogen compounds can then leave the body through urine or through bile and stool..

Liver → bile → intestine → stool
Or
Liver → bloodstream → kidneys → urine

What Can Affect Estrogen Metabolism?

Estrogen metabolism can be influenced by several physiological and lifestyle factors. Excess adipose tissue can contribute to increased estrogen production because adipose tissue contains enzymes which are  involved in estrogen formation. Alcohol consumption can also affect  estrogen metabolism and liver function.Dietary patterns, physical activity, metabolic health, bowel habits and gut microbial composition may also affect hormone metabolism.

Ayurveda and Estrogen Detoxification

Several Ayurvedic principles can be used to understand the broader idea of maintaining healthy metabolism and elimination.  Agni represents digestion and metabolic activity. When Agni functions properly, food and nutrients can be processed efficiently. Ama refers to improperly processed metabolic material described in Ayurveda as resulting from impaired digestion and metabolism. Yakrit (liver) is considered an important organ in the body’s metabolic processes. Meda Dhatu (adipose tissue) is also relevant because excess adipose tissue can influence hormonal physiology. Malavaha Srotas relate to the proper formation and elimination of waste products, while Artavavaha Srotas is associated with female reproductive functions. From an Ayurvedic perspective, maintaining healthy digestion, metabolism, tissue nourishment, and elimination may therefore be considered an important part of supporting overall hormonal health.

Herbs used for estrogen detox

Turmeric – Curcuma longa

Key constituents: Curcumin, demethoxycurcumin and bisdemethoxycurcumin.

Mode of action: Curcumin has antioxidant and anti-inflammatory properties and may influence several liver enzymes and cellular pathways that are involved in metabolism. Since the liver is the major site of estrogen metabolism, supporting normal hepatic function is relevant when discussing estrogen detoxification.

Flaxseed – Linum usitatissimum

Key constituents: Lignans, especially secoisolariciresinol diglucoside (SDG), and alpha-linolenic acid.

Mode of action: Flaxseed is particularly interesting because its lignans are converted by intestinal bacteria into enterolignans. These compounds have weak estrogen-like activity and can interact with estrogen receptors. They may also influence estrogen metabolism and its movement between the intestine and liver.

Broccoli – Brassica oleracea

Key constituents: Glucosinolates, sulforaphane and indole-3-carbinol.

Mode of action: Indole-3-carbinol and its metabolites influence estrogen metabolism, including the relative formation of different estrogen metabolites. Sulforaphane also activates cellular antioxidant and protective pathways. Broccoli sprouts are particularly rich sources of glucosinolate-derived compounds.

Green Tea – Camellia sinensis

Key constituents: Epigallocatechin gallate (EGCG), epicatechin, epigallocatechin and other catechins.

Mode of action: Green tea catechins have antioxidant properties and have been investigated for their effects on enzymes involved in estrogen metabolism.

Amalaki – Phyllanthus emblica

Key constituents: Emblicanin A, emblicanin B, gallic acid, ellagic acid and vitamin C.

Mode of action: Amalaki provides antioxidant compounds that may help protect cells from oxidative stress. In Ayurveda, it is considered a Rasayana and is traditionally used to support overall metabolic health.

Bhumyamalaki – Phyllanthus amarus

Key constituents: Phyllanthin, hypophyllanthin, lignans and flavonoids.

Mode of action: Bhumyamalaki has traditionally been associated with Yakrit (liver) support. Experimental studies have investigated its antioxidant and hepatoprotective effects. Because estrogen is extensively metabolized in the liver, maintaining normal hepatic function is an important part of healthy estrogen metabolism.

Haritaki – Terminalia chebula

Key constituents: Chebulagic acid, chebulinic acid, gallic acid and ellagic acid.

Mode of action: Haritaki is traditionally considered Anulomana, supporting normal bowel movement and elimination. This is relevant because estrogen metabolites can be excreted into the intestine through bile. Maintaining regular bowel function may therefore support normal elimination .

Guduchi – Tinospora cordifolia

Key constituents: Tinosporaside, cordifolioside, diterpenoid compounds and alkaloids.

Mode of action: Guduchi is traditionally described as Deepana, Pachana and Rasayana. Experimental research has investigated its antioxidant and hepatoprotective properties.

Pomegranate – Punica granatum

Key constituents: Punicalagins, ellagic acid, anthocyanins and other polyphenols.

Mode of action: Pomegranate polyphenols have antioxidant activity and may influence hormone-related pathways. Its polyphenols are also metabolized by gut bacteria, making the gut microbiome relevant to their biological effects.

Cinnamon – Cinnamomum verum

Key constituents: Cinnamaldehyde, cinnamic acid, eugenol and polyphenols.

Mode of action: Cinnamon has antioxidant and metabolic effects and has been studied particularly in relation to glucose and insulin metabolism.

Natural Ways to Support Healthy Estrogen Metabolism

Foods to Include

A balanced, fiber-rich diet can support digestion, bowel regularity, metabolic health, and the body’s normal hormone-processing pathways.

Cruciferous vegetables

Vegetables such as broccoli, cabbage, cauliflower, spinach and other green vegetables can be included regularly These vegetables contain glucosinolates and related compounds that have been studied for their influence on estrogen metabolism.

Fiber-rich foods

Whole grains, oats, barley, lentils, beans and chickpeas can help maintain good digestion and regular bowel movements. ,which is relevant because some estrogen metabolites are eliminated through the intestine.

Seeds

Flaxseeds are especially useful to include in the diet because they contain lignans, which are processed by gut bacteria and may influence estrogen metabolism. Other seeds  include chia seeds , sesame seeds and pumpkin seeds .

Fruits

Fruits such as apples, guava, berries, pomegranate and papaya provide fiber and antioxidants.

Foods and Habits to Limit

 Limiting the following can support overall metabolic and liver health:

  • Excess alcohol
  • Sugary beverages
  • Excess sweets and desserts
  • Highly processed foods
  • Frequent deep-fried foods
  • Excess refined carbohydrates
  • Processed meats
  • Excessive calorie intake

Yoga Asanas for Supporting Hormonal and Metabolic Health

Regular yoga and physical activity can support stress management, physical activity, metabolic health, sleep, and overall well-being.

Bhujangasana (Cobra Pose)

Bhujangasana involves gentle extension of the spine and can be included in a regular yoga routine. It may help improve flexibility and body awareness.

Setu Bandhasana (Bridge Pose)

This posture works the lower body and trunk and can be incorporated into a general fitness and yoga routine.

Malasana (Garland Pose)

Malasana involves a deep squat position and may support mobility of the hips and pelvis. It can also be useful as part of a routine aimed at maintaining regular physical activity..

Marjariasana-Bitilasana (Cat-Cow Pose)

This gentle movement improves spinal mobility and can be useful as a warm-up or relaxation practice.

Balasana (Child’s Pose)

Balasana is a gentle resting posture that can be used for relaxation and stress management.

Anulom Vilom Pranayama

Alternate-nostril breathing can be included as a relaxation practice. It may help promote calmness and mindful breathing, although it should not be presented as a method that directly removes estrogen.

Surya Namaskar

Surya Namaskar combines multiple movements and can provide a useful form of regular physical activity. It may be particularly useful when practiced according to the individual’s fitness level.

Myths about estrogen detox

Myth 1: Estrogen is harmful and should be removed completely.

Fact: Estrogen is an important hormone needed for many normal body functions. The aim is to maintain a healthy balance, not remove it completely.

Myth 2: Detox drinks can remove estrogen quickly.

Fact: No specific drink can quickly flush estrogen from the body. The liver and other organs naturally process and eliminate hormones.

Myth 3: Sweating removes extra estrogen.

Fact: Sweating mainly helps control body temperature. It is not a major way of removing estrogen.

Myth 4: More estrogen detox is always better.

Fact: The body needs the right amount of estrogen. Healthy hormone balance is more important than trying to remove as much estrogen as possible.

Myth 5: Constipation does not affect estrogen removal.

Fact: Some estrogen metabolites leave the body through stool. Regular bowel movements can therefore support normal elimination.

Myth 6: All hormonal symptoms mean estrogen is high.

Fact: Irregular periods, bloating, acne, breast tenderness and mood changes can have many different causes. They do not always mean high estrogen.

CONCLUSION

The body has its own system to manage estrogen, so there is no need for extreme detox programs or complete removal of this hormone. The main aim should be to keep the liver, digestive system and bowel function healthy so that estrogen can be processed and removed normally. Eating fresh foods, taking enough fiber, staying physically active, maintaining a healthy weight and getting proper sleep can support this process. Ayurvedic herbs may be used according to individual requirements to support digestion, metabolism and liver health. In Ayurveda, good Agni (digestion and metabolism) and proper elimination are considered important for maintaining balance in the body. Therefore, instead of focusing only on “detoxing estrogen,” a simple and balanced lifestyle with appropriate Ayurvedic support can help maintain healthy hormonal function.

Herbal Remedies of Squint – Causes, Symptoms, Diagnosis & Treatment

Abstract

Squint is a condition in which the eyes do not maintain proper alignment while looking at an object. The deviation may involve one or both eyes and can vary in direction, frequency, and severity. It may develop during childhood or appear later in life due to abnormalities involving the eye muscles, nerves, vision, or other underlying conditions. Persistent misalignment can interfere with binocular vision and, particularly in children, may affect the development of normal visual function. Clinical evaluation includes assessment of ocular alignment, visual acuity, eye movements, and binocular vision to identify the type and possible cause. Early assessment is important because timely intervention can help preserve visual development and improve ocular alignment and functional outcomes.

Squint

Statistics for Squint

  • Strabismus is estimated to affect around 1.81% of the global population.
  • Approximately 2% of children are affected by some form of squint.
  • Around 5% of the general population may have amblyopia (lazy eye), which can develop when childhood strabismus interferes with normal visual development.
  • Inward deviation of the eye represents approximately 45%–50% of reported strabismus cases.
  • Outward deviation accounts for roughly 28%–36% of cases.
  • Approximately 20%–30% of children undergoing strabismus surgery may require an additional procedure for residual or recurrent misalignment.

Interesting Facts about Squint

    • The eyes can point in different directions: Strabismus can affect one eye or alternate between both eyes, rather than always involving the same eye.
    • It is not always constant: Some forms appear only at certain times, such as when a person is tired, ill, or focusing at a particular distance.
    • Babies may temporarily appear cross-eyed: Occasional eye misalignment can occur during early infancy, but persistent deviation requires professional assessment.
    • Adults can develop it too: Squint is not exclusively a childhood condition and can appear for the first time during adulthood.
    • Eye alignment can change over time: A deviation that was previously controlled may become more noticeable or frequent as visual demands change.
    • The brain plays an important role: Normal binocular vision requires the brain to combine information from both eyes into a single visual experience.
    • The condition has a long history: Historical medical writings and artwork contain descriptions suggestive of eye misalignment, showing that strabismus has been recognized for centuries.

Introduction

Squint, medically termed strabismus, refers to an abnormal relationship between the alignment and movement of the two eyes. Under normal conditions, both eyes work together to maintain coordinated fixation on the same target, allowing the visual system to combine their information efficiently. In strabismus, this coordination is disturbed, resulting in a deviation of one eye relative to the other. The deviation may be inward, outward, upward, or downward and can occur continuously or intermittently. Squint is frequently recognized during childhood, when proper ocular alignment is particularly important for the development of binocular vision. However, it may also be identified for the first time in adults.

Types of Squint Based on the Direction of Eye Deviation

Esotropia (Inward Deviation)

The affected eye or eyes deviate toward the nose. It is commonly described as a crossed-eye appearance and may be present continuously or occur intermittently.

Exotropia (Outward Deviation)

The eye moves away from the nose toward the outer side of the face. The deviation may be more apparent during distance viewing, fatigue, or reduced visual attention.

Hypertropia (Upward Deviation)

One eye is positioned higher than the other, producing a vertical difference in ocular alignment. The upward deviation may remain constant or vary depending on the direction of gaze.

Hypotropia (Downward Deviation)

 One eye is positioned lower than the fellow eye. This represents a vertical misalignment and may occur alone or alongside other forms of strabismus.

Mixed Deviation

 In some individuals, horizontal and vertical deviations can occur together, producing a more complex pattern of ocular misalignment that requires detailed ophthalmic assessment.

Etiological Factors for Squint

Squint can arise from abnormalities affecting eye movement, vision, the nervous system, or the structures responsible for maintaining ocular alignment. Important etiological factors include:

Abnormal eye-muscle function

Weakness, overactivity, restriction, or poor coordination of the extraocular muscles can prevent the eyes from moving together accurately.

Refractive errors

Significant hypermetropia, myopia, or astigmatism can interfere with coordinated binocular vision and may contribute to ocular misalignment.

Cranial nerve disorders

Dysfunction of the third, fourth, or sixth cranial nerves, which control several extraocular muscles, can produce new-onset strabismus.

Amblyopia

Reduced visual development in one eye can weaken binocular coordination and may be associated with persistent ocular deviation.

Neurological disorders

Conditions affecting the brain, brainstem, or pathways controlling eye movements can lead to ocular misalignment.

Head injury

Trauma involving the head or orbit may damage ocular muscles or their nerve supply and subsequently cause strabismus.

Orbital abnormalities

Tumors, inflammation, fractures, or structural changes within the orbit can mechanically interfere with normal eye positioning.

Prematurity

Children born prematurely have a higher risk of developing strabismus, particularly when associated with other complications of prematurity.

Genetic predisposition

A family history of strabismus may increase susceptibility, suggesting that inherited factors contribute to its development.

Age-related changes

 New-onset strabismus in adults can occur with changes in ocular motor control, muscle function, or underlying neurological or systemic disease and requires appropriate evaluation.

Signs and Symptoms of Squint

The clinical presentation of squint (strabismus) varies according to the type, degree, and consistency of eye deviation. Some features are readily visible, while others reflect disturbances in binocular vision and visual coordination. The symptoms include:

Visible ocular misalignment

One eye may deviate inward, outward, upward, or downward instead of maintaining the same line of fixation as the other eye.

Intermittent deviation

The eyes may appear aligned at some times and become misaligned at others, particularly during fatigue, illness, or prolonged visual tasks.

Abnormal head positioning

Tilting, turning, or raising the chin may be used to achieve a more comfortable visual position or improve alignment.

Closing or covering one eye

A person may habitually close one eye during bright light or visually demanding activities to improve visual comfort.

Difficulty with binocular vision

Misalignment can interfere with the ability of both eyes to work together as a coordinated pair.

Double vision (diplopia)

Adults with newly developed strabismus may experience two images of the same object because the eyes are directed toward different points.

Reduced vision in one eye

Persistent childhood misalignment can be associated with amblyopia, in which vision fails to develop normally despite the absence of adequate structural explanation.

Eye strain during visual tasks

Sustained reading, screen use, or near work may become uncomfortable when maintaining coordinated fixation is difficult.

Diagnosis of Squint

It involves a systematic ophthalmic assessment to determine whether the eyes are misaligned, the direction and magnitude of deviation, visual function, and the underlying cause. The diagnostic assessment is as follows:

Medical and Ocular History

The clinician records the age at which the deviation was first noticed, its duration, and whether it is constant or intermittent. Previous eye problems, trauma, surgery, neurological disorders, and systemic illnesses are reviewed. A family history of strabismus, amblyopia, or significant refractive errors is also considered.

Ocular Alignment Examination

The position of both eyes is observed while the patient looks at a fixation target. The examiner determines whether the deviation is horizontal, vertical, or combined.

Visual Acuity Assessment

Vision is measured separately for each eye and, when appropriate, with both eyes together. Differences in visual acuity between the eyes can suggest amblyopia or an underlying ocular disorder.

Hirschberg Test

A light is directed toward the patient’s eyes and the position of the corneal light reflex is observed. Differences in the location of the reflex between the two eyes provide an initial indication of ocular misalignment.

Measurement of Deviation

The magnitude of ocular deviation is measured using techniques such as prism cover testing. The result is commonly recorded in prism diopters (PD) and helps determine the severity and guide treatment planning.

Binocular Vision Assessment

Stereopsis (depth perception), fusion, and sensory cooperation may be assessed to understand the functional impact of the deviation.

Neurological and Systemic Evaluation

Newly developed strabismus, particularly in adults, may require assessment of cranial nerve function, pupils, facial movements, and other neurological findings.

Management of Squint

Management of squint is individualized according to the age of the patient, type and magnitude of deviation, visual acuity, binocular function, underlying cause, and presence of amblyopia. The management approaches include:

Corrective Eyewear

Appropriate spectacles are prescribed when refractive errors contribute to the deviation. Correcting significant hypermetropia, myopia, or astigmatism may improve ocular alignment and visual function.

Prism Correction

Prism lenses can redirect incoming light and reduce the visual effect of certain ocular deviations. They may be useful in selected patients, particularly those experiencing diplopia.

Vision and Orthoptic Therapy

Selected patients may benefit from exercises designed to improve binocular coordination, convergence, or fusional control. These approaches are particularly relevant to specific forms of convergence insufficiency and binocular vision disorders.

Botulinum Toxin

Botulinum toxin injections may be used in selected cases to temporarily weaken a specific extraocular muscle. It can be considered in certain adult or acute-onset strabismus cases and in situations where conventional surgery may not be immediately appropriate.

Strabismus Surgery

The procedure generally involves repositioning or altering the tension of selected extraocular muscles to improve eye alignment. Depending on the deviation, one or several muscles may be treated.

Ayurveda Insights

From an Ayurvedic perspective, squint may be viewed through the concepts of Drishti (vision), Netra (eye), Dosha, and the functional coordination of ocular tissues. Classical Ayurveda describes the eyes as closely associated with Alochaka Pitta, which supports visual perception, while Vata is responsible for movement and coordination. Disturbance of these functional principles may be considered in understanding abnormal ocular movement or alignment. Tarpana, Netra Parisheka, Seka, and suitable local therapies are traditionally described for maintaining ocular comfort and supporting eye health, while internal management may be selected according to the individual’s Dosha and clinical condition. Appropriate nutrition, adequate sleep, protection from excessive visual strain, and regular daily routines may also support overall ocular wellbeing.

Pathogenesis of Squint

In Ayurvedic interpretation, the development of ocular deviation can be understood through the disturbance of Netra-related functions and Vata-dominant neuromuscular activity. Vitiated Vata may interfere with the balanced action of the structures responsible for coordinated eye movement, resulting in unequal positioning of the visual axes. Alochaka Pitta, which governs the functional aspect of vision, may become secondarily affected when ocular coordination is disturbed. With continued imbalance, the normal relationship between Drishti, ocular movement, and fixation may become altered, producing persistent or intermittent deviation. Ayurveda also emphasizes the role of Dhatvagni and tissue nourishment; inadequate nourishment of the relevant ocular and neuromuscular structures may impair their functional efficiency.

Herbal Remedies for Squint by Planet Ayurveda

Planet Ayurveda is a well-established Ayurvedic healthcare organization that works to promote the ancient knowledge of Ayurveda through natural remedies and holistic health solutions. The company develops a wide range of herbal formulations using pure, high-quality ingredients and standardized herbal extracts, with a focus on maintaining safety, authenticity, and effectiveness. Following the principles of classical Ayurveda, Planet Ayurveda aims to support overall health by addressing the underlying causes of health concerns and encouraging balance in the body, mind, and emotions. With an emphasis on quality, natural ingredients, and traditional approaches supported by modern research, the organization works toward making Ayurvedic wellness solutions available globally. We will explore various herbal approaches used for the management of Squint according to Ayurvedic principles. The herbal formulations are:

  1. Tapyadi Loha
  2. Yastimadhu Ghan Vati
  3. Sameer Pannag Ras

Product description

1. Tapyadi Loha

It is a classical Ayurvedic formulation containing Triphala—Amalaki (Phyllanthus emblica), Haritaki (Terminalia chebula), and Vibhitaki (Terminalia bellirica)—along with Trikatu—Pippali (Piper longum), Maricha (Piper nigrum), and Shunthi (Zingiber officinale). It also contains Chitrakmool (Plumbago zeylanica), Vidanga (Embelia ribes), Pippalimula (Piper longum), Devadaru (Cedrus deodara), Daruharidra (Berberis aristata), Dalchini (Cinnamomum verum), and Chavya (Piper retrofractum). Its ingredients possess predominantly Deepana (appetite-enhancing) and Pachana (digestive) properties, which may help maintain proper Agni and support the nourishment of body tissues. From an Ayurvedic perspective, maintaining healthy tissue metabolism may indirectly support the functional health of the ocular system.

Dosage: 1 tablet twice a day with warm water.

2. Yastimadhu Ghan Vati

Its principal ingredient, Yashtimadhu (Glycyrrhiza glabra), is traditionally described as Madhura, Guru, and Snigdha, with nourishing and soothing properties. From an Ayurvedic perspective, Yashtimadhu may support Vata-Pitta balance, promote proper tissue nourishment, and help maintain the functional health of the Netra (ocular system). Its Rasayana and Brimhana attributes may be useful as part of an individualized regimen aimed at supporting ocular strength and overall nourishment.

Dosage: 1 tablet twice a day.

3. Sameer Pannag Ras

It may be considered in an Ayurvedic approach to squint (strabismus) as a specialized herbo-mineral formulation intended to support Netra Bala (ocular strength) and functional balance. It contains Shuddha Gandhak (purified sulfur), Ghrit Kumari Ras (Aloe vera juice), Shuddha Mansheel (purified realgar), Shuddha Parad (purified mercury), Hartal (purified orpiment), and Swarna (gold). From an Ayurvedic perspective, its formulation may be considered for supporting Vata-Pitta balance, tissue nourishment, and overall ocular function.

Dosage: 125 mg once a day after meals with warm water or honey.

Ayurvedic Procedures in Management of Squint

Bahya Trataka

  • Bahya Trataka is a traditional yogic practice involving steady, focused gazing at an external object. In the context of squint (strabismus), it may be considered a supportive visual practice aimed at improving concentration, visual awareness, and voluntary control of eye movements.
  • The practitioner should sit comfortably in a stable position with the spine erect and select a stationary object placed at a comfortable distance, such as a small mark or symbol on a wall.
  • The object should be clearly visible without causing eye strain. After relaxing the body and maintaining natural breathing, the practitioner gently directs both eyes toward the selected point and attempts to maintain a steady gaze without excessive blinking or forceful contraction of the eye muscles.
  • Initially, the practice may be performed for a short duration, followed by relaxed blinking and closing of the eyes. With gradual adaptation, the duration can be increased according to comfort.
  • From an Ayurvedic perspective, Trataka may support Indriya Bala (sensory strength), concentration, and functional coordination of the Netra (eyes).

Netra Tarpana

  • Netra Tarpana is a classical ocular procedure in which medicated ghrita (clarified butter) or another suitably selected preparation is retained around the eyes for a prescribed period.
  • In an Ayurvedic approach to squint (strabismus), it may be considered as a supportive procedure for maintaining Netra Bala (ocular strength) and promoting nourishment of the structures surrounding the eyes.
  • The procedure is traditionally selected according to Dosha, Prakriti, age, ocular condition, and overall health. A medicated ghrita is placed within a properly constructed ring around the closed eyes, allowing the preparation to remain in contact with the periocular region for a specified duration under supervision.
  • From an Ayurvedic perspective, Netra Tarpana may help maintain ocular comfort, reduce dryness and fatigue, and support normal sensory function.

Shashtika Shali Pinda Sweda

  • Shashtika Shali Pinda Sweda is a classical Ayurvedic Swedana (sudation and fomentation) procedure in which warm boluses prepared from Shashtika Shali rice are gently applied to selected areas of the body using a nourishing herbal milk decoction.
  • Shashtika Shali is a special variety of rice traditionally regarded as Brimhana (nourishing), Balya (strength-promoting), and Vata-pacifying.
  • In an Ayurvedic approach to squint (strabismus), this therapy may be considered as a supportive measure when Vata predominance, muscular weakness, stiffness, or impaired neuromuscular coordination is associated with the clinical presentation.
  • The warm, nourishing application may help promote local relaxation, tissue nourishment, and functional comfort.
  • The procedure is generally performed by dipping prepared rice boluses in a warm milk-based decoction and applying them with gentle, rhythmic movements over appropriate regions, according to the individual’s condition.
  • It should be selected according to Prakriti, Dosha, Bala, age, and clinical status.

Conclusion

Successful management of squint requires timely recognition, individualized assessment, and a treatment plan based on the underlying cause, age, visual status, and degree of ocular deviation. Regular monitoring is particularly important in children to protect binocular vision and reduce the risk of long-term visual impairment. Supportive measures should focus on maintaining ocular comfort, healthy visual habits, adequate nutrition, and overall wellbeing. From an Ayurvedic perspective, individualized care based on Dosha balance, Netra Bala, Agni, and proper daily routine may be incorporated as complementary support.

Upadoz / Upadacitinib and Psoriatic Arthritis: Targeting Inflammation at Its Source

Abstract

Psoriatic arthritis (PsA) is a chronic inflammatory condition characterized by persistent joint inflammation, pain, stiffness, and progressive structural damage, often occurring alongside psoriasis. Upadacitinib (Upadoz) represents a targeted therapeutic approach that acts primarily through inhibition of Janus kinase 1 (JAK1), a key intracellular pathway involved in cytokine-mediated inflammatory signaling. By interfering with JAK–STAT signaling, upadacitinib can reduce downstream inflammatory activity and help control multiple manifestations of PsA. Clinical studies, including the SELECT-PsA trials, have demonstrated improvements in joint symptoms, physical function, and other disease manifestations among appropriately selected patients. Its oral once-daily administration also provides a convenient treatment option

Upadoz / Upadacitinib and Psoriatic Arthritis

Statistics for Psoriatic Arthritis

  • Psoriatic arthritis affects around 0.1%–0.2% of the worldwide population.
  • Estimates place the prevalence at approximately 112–130 cases per 100,000 adults.
  • Around 3–41 new cases per 100,000 person-years are reported globally.
  • Rates tend to be higher in Europe and North America than in Asia and South America.
  • Nearly 1 in 5 people with psoriasis may eventually develop psoriatic arthritis.
  • Studies report considerable variation, with approximately 6%–41% of psoriasis patients developing joint disease.
  • In about 68% of cases, psoriasis develops before arthritis symptoms.
  • Approximately 15% experience skin and joint manifestations around the same time.
  • About 17% develop joint symptoms before noticeable skin lesions.

Interesting Facts about Psoriatic Arthritis

  • Skin and joints are connected: Psoriatic arthritis can affect both the skin and musculoskeletal system, although joint disease may sometimes occur without obvious psoriasis.
  • Different people show different patterns: Psoriatic arthritis does not follow one fixed pattern, which can make diagnosis challenging.
  • It is not simply “wear and tear”: Unlike osteoarthritis, PsA is an immune-mediated inflammatory arthritis.
  • Arthritis can precede psoriasis: In a minority of patients, joint inflammation appears before any visible skin lesions, sometimes making the diagnosis difficult.
  • The jaw can be affected: PsA may involve the temporomandibular joint (TMJ), potentially causing jaw pain, stiffness, or difficulty opening the mouth.
  • Hidden inflammation may exist despite limited skin disease: The severity of psoriasis on the skin does not necessarily reflect the extent of underlying musculoskeletal involvement.
  • It can mimic several other conditions: Depending on the joints and tissues involved, PsA may resemble rheumatoid arthritis, gout, osteoarthritis, or other spondyloarthropathies, making clinical pattern recognition important.

Introduction

Psoriatic arthritis (PsA) is a heterogeneous, chronic inflammatory musculoskeletal disease associated with psoriasis and characterized by involvement of peripheral joints, entheses, digits, and axial structures. The underlying immunopathology involves a complex network of cytokines and intracellular signaling pathways that sustain synovial inflammation, enthesitis, osteoproliferation, and bone erosion. Persistent inflammatory activity may consequently result in functional impairment, structural joint damage, and deterioration in quality of life. The clinical heterogeneity of PsA also presents challenges in achieving comprehensive disease control, particularly when multiple domains of disease activity coexist. Advances in understanding the molecular mechanisms underlying PsA have facilitated the development of targeted synthetic disease-modifying antirheumatic drugs (tsDMARDs). Among these, upadacitinib (Upadoz) is an orally administered, selective Janus kinase 1 (JAK1) inhibitor designed to interfere with intracellular cytokine signaling. JAK1 participates in signal transduction mediated by several cytokines implicated in PsA pathogenesis, including pathways associated with interleukin and interferon activity. Pharmacological inhibition of JAK1 therefore provides a mechanism for attenuating multiple inflammatory signals simultaneously.

Causes and Risk Factors of Psoriatic Arthritis

Psoriatic arthritis does not have a single identifiable cause. It is believed to develop through an interaction between genetic susceptibility, immune dysregulation, and environmental or mechanical triggers.

Genetic predisposition

A family history of psoriasis or PsA increases susceptibility. Several genetic variants, particularly within immune-regulatory genes, have been associated with disease development.

Immune-system dysregulation

 Abnormal activation of immune pathways promotes the release of inflammatory mediators, including TNF-α, IL-17, and IL-23, contributing to joint and entheseal inflammation.

Psoriasis

The presence of cutaneous or nail psoriasis is the strongest established clinical risk factor for developing PsA, although arthritis can occasionally precede skin manifestations.

Environmental triggers

Infections, physical trauma, psychological stress, and other environmental influences may contribute to disease onset or flare in genetically predisposed individuals.

Joint or tissue injury

Mechanical stress or previous trauma may initiate inflammation at susceptible sites, particularly around entheses.

Obesity and metabolic factors

Excess adiposity is associated with an increased likelihood of PsA and may also contribute to greater inflammatory activity.

Smoking and lifestyle factors

Tobacco exposure and certain lifestyle-related factors have been investigated as potential modifiers of PsA risk and disease severity.

Gut–immune interactions

Alterations in the intestinal microbiome and mucosal immune responses are being investigated for their possible contribution to PsA development.

Signs and Symptoms of Psoriatic Arthritis

Psoriatic arthritis can present differently from one person to another. The pattern and intensity of symptoms may also change over time. The symptoms include:

Joint pain and tenderness

Affected joints may become painful, particularly during movement or prolonged activity. Tenderness can occur around the joint as well as in the surrounding tissues.

Joint swelling

Inflammation may cause visible swelling and a feeling of fullness around affected joints. Swelling can involve one or several joints.

Morning stiffness

Stiffness after waking or following prolonged inactivity is common. It may persist for some time and often improves as the joints become mobile.

Reduced range of motion

Inflammation, pain, and swelling can restrict normal joint movement, affecting activities such as walking, gripping, climbing stairs, or bending.

Dactylitis

 An entire finger or toe may become diffusely swollen because inflammation involves multiple structures within the digit. This characteristic presentation is often described as a “sausage digit.”

Enthesitis

Inflammation can occur where tendons or ligaments attach to bone. Common sites include the heel, achilles tendon, sole of the foot, and elbow, producing localized pain and tenderness.

Lower back or spinal symptoms

Some individuals develop inflammatory back pain involving the spine or sacroiliac joints. Stiffness may be more noticeable after rest and may improve with physical activity. .

Psoriatic skin lesions

Red, scaly, well-defined plaques may occur, commonly affecting the scalp, elbows, knees, or other areas.

Knee, ankle, or other large-joint involvement

PsA may affect larger peripheral joints, producing swelling, pain, stiffness, and functional limitations.

Asymmetrical joint involvement

 Unlike some other inflammatory arthritides, PsA may affect different joints on opposite sides of the body, although symmetrical patterns can also occur.

Episodes of worsening

Symptoms may fluctuate, with periods of increased inflammation or flares followed by periods when symptoms become less pronounced.

Progressive functional impairment

Persistent untreated inflammation can eventually interfere with mobility, hand function, work, exercise, and other everyday activities.

Nail abnormalities

Psoriatic arthritis may be accompanied by nail pitting, ridging, discoloration, thickening, crumbling, or separation of the nail from its underlying bed.

How Upadoz Works for the Management of Psoriatic Arthritis

Upadoz (upadacitinib) is a targeted oral therapy belonging to the Janus kinase (JAK) inhibitor class. Its principal pharmacological action is directed toward JAK1, an intracellular kinase involved in transmitting signals generated by several cytokines implicated in immune-mediated inflammation. Rather than neutralizing a cytokine outside the cell, upadacitinib interferes with the intracellular signaling machinery responsible for translating cytokine–receptor interactions into cellular responses.

Inhibition of JAK–STAT signaling

Following cytokine binding to its cellular receptor, JAK proteins become activated and phosphorylate signal transducers and activators of transcription (STATs). Activated STATs subsequently influence gene transcription within the nucleus, promoting immune-cell activation and inflammatory responses. Upadacitinib inhibits JAK activity and thereby reduces STAT phosphorylation and downstream transcriptional signaling.

Preferential JAK1 activity

Upadacitinib demonstrates greater inhibitory potency toward JAK1 than JAK2, JAK3, and TYK2. This pharmacological selectivity is relevant because JAK1 participates in signaling pathways associated with several inflammatory cytokines. However, JAK selectivity should not be interpreted as complete exclusivity; cytokine receptors frequently utilize JAK combinations, allowing JAK1 inhibition to influence multiple signaling pathways.

Suppression of inflammatory signaling

Psoriatic arthritis involves dysregulated immune signaling that contributes to synovitis, enthesitis, dactylitis, and other inflammatory manifestations. By attenuating JAK-dependent cytokine signaling, upadacitinib can reduce the intracellular inflammatory response and consequently decrease disease activity.

Impact across multiple disease domains

The therapeutic significance of JAK1 inhibition extends beyond reduction of joint inflammation. Clinical studies of upadacitinib in PsA have demonstrated improvements in peripheral arthritis, physical function, enthesitis, dactylitis, and psoriasis-related manifestations, supporting its role as a treatment capable of addressing several domains of this heterogeneous disease.

Thus, Upadoz acts at an important intracellular signaling checkpoint, interrupting cytokine-driven communication before it culminates in sustained inflammatory activity. This targeted mechanism provides the pharmacological basis for its use in appropriately selected patients with active PsA.

Who May Benefit from Upadacitinib?

Upadacitinib may be considered for patients with active psoriatic arthritis (PsA) when conventional treatment does not provide adequate disease control or cannot be tolerated. Patient selection should be individualized according to disease severity, affected domains, previous therapies, comorbidities, and safety considerations.

Patients with active PsA despite DMARD therapy

Individuals who continue to experience clinically significant joint inflammation, pain, stiffness, or functional impairment despite disease-modifying antirheumatic drugs may be candidates for targeted therapy.

Patients with inadequate response to biologic therapy

Clinical evidence supports upadacitinib in patients whose PsA remains active despite treatment with one or more biologic DMARDs. SELECT-PsA 2 specifically evaluated this treatment setting and demonstrated significantly greater clinical responses than placebo.

Patients with inadequate response or intolerance to TNF inhibitors

Current U.S. prescribing information identifies active PsA with inadequate response or intolerance to one or more TNF blockers as an indication for upadacitinib.

Patients with multiple disease manifestations

Upadacitinib may be particularly relevant when PsA involves several domains simultaneously, such as peripheral arthritis, enthesitis, dactylitis, axial symptoms, and psoriasis. Clinical trials have demonstrated improvements across several of these manifestations.

Patients requiring an oral targeted treatment

Upadacitinib is administered orally once daily, providing an alternative to injectable biologic therapies for appropriately selected patients.

Patients requiring substantial disease control

Trial data have shown improvements in joint responses, physical function, psoriasis outcomes, and achievement of minimal disease activity, supporting its role in patients with clinically meaningful disease burden.

Importantly, upadacitinib is not appropriate for every patient with PsA. Before initiation, clinicians should evaluate infection risk, tuberculosis and viral hepatitis status where appropriate, blood counts, liver function, cardiovascular and thromboembolic risk, malignancy risk, pregnancy considerations, and potential drug interactions. The drug should also not be combined with other JAK inhibitors or biologic DMARDs. Therefore, the potential benefit of upadacitinib is greatest when its targeted mechanism, clinical profile, and safety considerations align with the individual patient’s disease characteristics and previous treatment history.

Ayurveda Insights

From an Ayurvedic perspective, psoriatic arthritis may be understood through the interplay of Vata and Pitta doshas with impaired Agni and accumulation of Ama, particularly when inflammatory manifestations involve the joints, skin, and soft tissues. The clinical picture may be considered in relation to Amavata when prominent features include pain, stiffness, swelling, and systemic inflammatory activity, while associated skin manifestations may reflect disturbances involving Rakta and Twak dhatus. Ayurvedic management focuses on identifying causative dietary and lifestyle factors, supporting Agni, reducing Ama, restoring doshic balance, and maintaining healthy tissue metabolism.

Pathogenesis of Psoriatic Arthritis

Ayurvedic interpretation of psoriatic arthritis can be developed through the concept of Samprapti, emphasizing the progression of pathological changes from the initial doshic disturbance to localization in specific tissues. Persistent exposure to causative factors may initiate Dosha Prakopa, followed by alteration of normal tissue nourishment and circulation. The disturbed Doshas subsequently gain access to susceptible Kha-Vaigunya (vulnerable sites), particularly the joints, tendons, and skin. Vata facilitates the movement and localization of the aggravated Doshas, while Pitta may intensify inflammatory and erythematous manifestations. In the musculoskeletal system, involvement of Sandhi, Asthi, and Majja, together with impaired function of Snayu, can account for pain, stiffness, swelling, and restricted movement. Concurrent involvement of Rakta and Twak provides an Ayurvedic framework for associated cutaneous manifestations.

Ayurvedic Alternatives for Upadoz/Upadacitinib by Planet Ayurveda

Planet Ayurveda is a well-established Ayurvedic healthcare organization that works to promote the ancient knowledge of Ayurveda through natural remedies and holistic health solutions. The company develops a wide range of herbal formulations using pure, high-quality ingredients and standardized herbal extracts, with a focus on maintaining safety, authenticity, and effectiveness. Following the principles of classical Ayurveda, Planet Ayurveda aims to support overall health by addressing the underlying causes of health concerns and encouraging balance in the body, mind, and emotions. With an emphasis on quality, natural ingredients, and traditional approaches supported by modern research, the organization works toward making Ayurvedic wellness solutions available globally. We will explore various herbal approaches used for the management of Psoriatic Arthritis  according to Ayurvedic principles. The herbal formulations are:

  1. Boswellia Curcumin
  2. Coral Calcium Complex
  3. Bone Support
  4. Yograj Guggul

Herbal Remedies For Psoriatic Arthritis

Buy Now Herbal Remedies For Psoriatic Arthritis

Buy NowHerbal Remedies For Psoriatic Arthritis

Product description

1. Boswellia Curcumin

These contain Brahmi (Bacopa monnieri) and Ashwagandha (Withania somnifera), two traditionally used Ayurvedic herbs associated with mental and nervous-system support. In the context of Seasonal Affective Disorder, this formulation may be considered as a supportive Ayurvedic approach for maintaining mental balance, coping with stress, and supporting healthy sleep and cognitive function during seasonal changes. Brahmi is traditionally valued as a Medhya Rasayana (cognitive rejuvenative), while Ashwagandha is regarded as a Rasayana with adaptogenic properties.

Dosage: 2 capsules twice a day after meals with plain water.

2. Coral Calcium Complex

These contain Ashwagandha (Withania somnifera), an Ayurvedic Rasayana (rejuvenative herb) traditionally used to support resilience, mental balance, and overall wellbeing. In the context of Seasonal Affective Disorder, Ashwagandha may be considered as a supportive Ayurvedic option for individuals experiencing stress, disturbed sleep, low energy, or difficulty adapting to seasonal changes. Its traditional use is particularly associated with promoting calmness and supporting healthy nervous-system function.

Dosage: 1 capsule twice a day after meals with plain water.

3. Bone Support

It contains a combination of Ashwagandha (Withania somnifera), Brahmi (Bacopa monnieri), Licorice (Glycyrrhiza glabra), Green Tea (Camellia sinensis), Ginger (Zingiber officinale), and Cinnamon (Cinnamomum verum). In an Ayurvedic supportive approach to Seasonal Affective Disorder, this herbal tea may be incorporated into a wellness routine aimed at maintaining mental calmness, relaxation, and daily balance during seasonal changes. Ashwagandha and Brahmi are traditionally valued for supporting mental wellbeing, while ginger and cinnamon are traditionally used to support digestion. Green tea provides a mild source of caffeine and antioxidants.

Dosage: 1 cup daily.

4. Yograj Guggul

It is a classical Ayurvedic polyherbal formulation containing Commiphora mukul (Guggulu), Plumbago zeylanica (Chitraka), Emblica officinalis (Amalaki), Cyperus rotundus (Musta), Terminalia bellirica (Bibhitaki), Piper longum (Pippali), Carum copticum, Tribulus terrestris, and several other botanicals. In Ayurvedic practice, its combination is traditionally used in disorders involving joint stiffness, pain, and impaired musculoskeletal function. The formulation may therefore provide supportive care for musculoskeletal symptoms associated with PsA, particularly discomfort and restricted mobility.

Dosage: 1 tablet twice a day with lukewarm water.

Conclusion

Upadacitinib has emerged as an important targeted option for achieving broader disease control in patients with active psoriatic arthritis. Its selective JAK1-directed activity provides a pharmacological means of interrupting several cytokine-dependent inflammatory pathways. Its oral administration may also offer practical advantages for appropriately selected patients. Overall, upadacitinib represents a significant advancement in targeted PsA management, particularly when sustained suppression of multidimensional inflammatory activity remains difficult to achieve.

Herbal Remedies of Seasonal Affective Disorder (SAD) – Causes, Symptoms, Diagnosis & Treatment

Abstract

Seasonal Affective Disorder (SAD) is a form of recurrent mood disturbance in which depressive symptoms appear during a particular season and improve when the season changes. It is commonly associated with reduced exposure to natural daylight, especially during autumn and winter, and may present with persistent sadness, low motivation, fatigue, increased sleep, changes in appetite, difficulty concentrating, and social withdrawal. Alterations in the body’s circadian rhythm, melatonin secretion, serotonin activity, and sleep-wake cycle may contribute to its development. Although SAD is often considered a subtype of major depressive disorder, its predictable seasonal pattern distinguishes it from many other depressive conditions. Diagnosis requires careful assessment of the timing, duration, severity, and recurrence of symptoms while excluding other medical or psychiatric causes.

Seasonal Affective Disorder (SAD)

Statistics for Seasonal Affective Disorder

  • SAD affects approximately 1%–10% of the general population.
  • Pooled prevalence is about 5.01%, while subsyndromal SAD is around 9.37%.
  • Summer-pattern SAD accounts for approximately 0.57%.
  • SAD may represent around 10% of diagnosed depressive episodes.
  • Symptoms generally persist for 4–5 months each year.
  • SAD most commonly begins during young adulthood, particularly between 18 and 30 years.

Interesting Facts about Seasonal Affective Disorder

  • It can follow a calendar: SAD often returns around the same time each year, making its pattern surprisingly predictable.
  • Location matters: SAD tends to be more common in regions with greater seasonal changes in daylight.
  • Summer SAD exists: SAD is not limited to winter; a smaller group of people experience a seasonal pattern during summer.
  • It can occur in children: Although commonly recognized in adults, seasonal mood changes can also affect children and adolescents.
  • It is more than the “winter blues”: SAD is a clinically recognized condition, whereas ordinary wintertime low mood may not meet diagnostic criteria.
  • Daylight can influence biological timing: Seasonal changes in daylight can interact with the body’s internal clock, which helps explain why SAD follows a seasonal rhythm.
  • The pattern can change: A person’s seasonal mood pattern may vary over different stages of life rather than remaining identical every year.
  • Geography does not tell the whole story: Latitude, climate, lifestyle, individual susceptibility, and access to daylight can all contribute to differences in how frequently SAD is reported.

Introduction

Seasonal Affective Disorder (SAD) is a clinically recognized mood disorder characterized by a recurring relationship between depressive episodes and a particular time of the year. Unlike depressive conditions that may occur without a recognizable seasonal pattern, SAD follows a temporal rhythm, with periods of emotional disturbance occurring during specific months and remission during other parts of the year. This recurring nature makes seasonality an important component of clinical assessment. SAD is most commonly associated with the autumn and winter months, although a smaller proportion of individuals experience symptoms during spring or summer. Its occurrence varies across geographical regions, and differences in daylight exposure across seasons have contributed to considerable interest in the relationship between environmental changes and mental health. The condition may influence daily functioning, interpersonal relationships, academic or professional performance, and overall quality of life.

Causes and Risk Factors of Seasonal Affective Disorder

This disorder develops through a combination of biological, environmental, genetic, and lifestyle-related factors. The causes and risk factors are as follows in detail:

Seasonal changes in daylight

Reduced daylight during certain seasons may affect brain systems involved in mood regulation and biological timing.

Circadian rhythm disruption

Changes in the light-dark cycle can disturb the body’s internal biological clock and alter normal sleep-wake regulation.

Altered serotonin activity

Seasonal changes may influence serotonin pathways involved in emotional regulation, potentially contributing to depressive symptoms in susceptible individuals.

Melatonin changes

Variations in light exposure can affect melatonin production and timing, influencing sleep patterns and circadian regulation.

Genetic susceptibility

A family history of depression, bipolar disorder, or SAD may increase an individual’s vulnerability.

Female sex

SAD has been reported more frequently among women than men, although the reasons for this difference remain incompletely understood.

Higher latitude

Living farther from the equator, where seasonal differences in daylight are greater, is associated with higher reported rates of winter-pattern SAD.

Bipolar disorder

People with bipolar disorder may experience a seasonal pattern in the timing of depressive or manic/hypomanic episodes.

Environmental and lifestyle factors

Seasonal changes in daily routine, physical activity, social interaction, and outdoor exposure may contribute to vulnerability in susceptible individuals.

Signs and Symptoms of Seasonal Affective Disorder

The clinical presentation of SAD can extend beyond ordinary low mood. Its recurring seasonal pattern and distinctive changes in biological and behavioral functioning are particularly important when recognizing the disorder. The signs and symptoms include:

Atypical depressive features

Winter-pattern SAD may show increased sleep, increased appetite, carbohydrate cravings, and weight gain rather than the reduced sleep and appetite often associated with typical depression.

Seasonal hypersomnia

A person may sleep substantially longer than usual yet continue to feel unrefreshed or excessively sleepy during the day.

Season-linked energy shift

A noticeable reduction in physical and mental drive may develop during the affected season, often interfering with normal daily activities.

Carbohydrate-focused cravings

Some individuals develop a strong preference for carbohydrate-rich foods, particularly during the colder or darker months.

Seasonal social withdrawal

Individuals may progressively reduce social interaction and participation in activities that they normally maintain.

Distinctive cognitive slowing

Thinking, concentration, decision-making, and mental responsiveness may feel noticeably slower during the affected season.

Seasonal hypersensitivity to environmental change

Mood and functioning may fluctuate noticeably as daylight duration and seasonal conditions change.

Functional impairment with repetition

The symptoms become clinically significant when they repeatedly interfere with occupational, academic, interpersonal, or everyday functioning across seasonal cycles.

Summer-pattern presentation

Although less common, summer SAD can present with a different pattern, including reduced sleep, decreased appetite, weight loss, agitation, and increased restlessness.

Diagnosis of Seasonal Affective Disorder

The diagnosis of Seasonal Affective Disorder (SAD) is primarily clinical and depends on identifying a consistent relationship between depressive episodes and a particular season. There are various diagnostic tests that are as follows:

Clinical History

The clinician records the onset, duration, severity, and recurrence of depressive symptoms. Changes in mood, sleep, appetite, energy, concentration, and daily functioning are assessed.

Assessment of Winter or Summer Pattern

Winter pattern may identify hypersomnia, increased appetite, carbohydrate cravings, and seasonal weight gain.  Summer patterns may reveal insomnia, reduced appetite, weight loss, agitation, or increased restlessness.

Symptom Questionnaires

Standardized depression or SAD-related questionnaires may be used to measure symptom severity and support the clinical assessment. Questionnaires are supportive tools rather than substitutes for professional diagnosis.

Functional Assessment

The clinician evaluates whether seasonal symptoms interfere with work, education, relationships, self-care, or everyday responsibilities. This helps distinguish clinically significant SAD from temporary seasonal changes in mood.

Psychiatric Evaluation

Current or previous episodes of major depression and bipolar disorder should be explored because SAD can occur in association with these conditions.

Management of Seasonal Affective Disorder

It should be individualized according to the seasonal pattern, severity of depression, functional impairment, previous episodes, and coexisting psychiatric or medical conditions. The management may require various approaches like:

Bright Light Therapy

It is a major treatment for winter-pattern SAD. A light box providing approximately 10,000 lux is commonly used. It is generally used in the morning, often for about 20–45 minutes daily, according to clinical guidance and the device’s instructions. The device should be designed specifically for SAD and should filter out potentially harmful ultraviolet (UV) radiation.

Cognitive Behavioral Therapy

It can help modify negative seasonal thoughts and unhelpful behavioral patterns. CBT for SAD may incorporate behavioral activation, encouraging regular engagement in meaningful activities. It can also help improve coping skills, stress management, sleep habits, and adherence to healthy routines.

Antidepressant Medications

These may be considered when symptoms are moderate to severe, persistent, or inadequately controlled with non-drug approaches. Bupropion extended-release has been used for prevention of recurrent seasonal depressive episodes. Selective serotonin reuptake inhibitors (SSRIs) and other antidepressants may also be considered depending on the clinical presentation.

Vitamin D Assessment

Vitamin D supplementation may be considered particularly in winter-pattern SAD when deficiency is present. Spending time outdoors during daylight hours can increase exposure to natural light. Morning outdoor activity may be incorporated into the daily routine, particularly during seasons with reduced daylight.

Structured Sleep Routine

Maintaining consistent sleep and wake times can help support regular circadian rhythms. Excessive daytime sleeping and prolonged naps should generally be avoided when they worsen the sleep-wake pattern.

Management of Summer-Pattern SAD

It generally focuses on evidence-based treatments for depression, including psychotherapy and appropriate medication when indicated.

Social and Behavioral Support

Maintaining regular contact with family, friends, colleagues, and supportive social networks can help counter seasonal withdrawal. Relaxation practices such as meditation, yoga, and stress-management techniques may complement the primary treatment plan.

Ayurveda Insights

From an Ayurvedic perspective, Seasonal Affective Disorder can be understood through the interaction of Manas (mind), Dosha, Agni (metabolic and digestive function), and seasonal changes (Ritucharya). The transition between seasons may influence Vata and Kapha, particularly when changes in coldness, dryness, reduced sunlight, inactivity, and daily routine disturb the body’s physiological balance. Kapha aggravation may be associated with heaviness, lethargy, excessive sleep, and reduced motivation, while Vata imbalance may contribute to mental restlessness, irregular sleep, and emotional instability. Ayurveda also emphasizes the role of Sattva (mental clarity and balance) and considers regular sleep, appropriate diet, physical activity, exposure to natural daylight, meditation, yoga, Abhyanga (oil massage), and adherence to seasonal routines as supportive measures for maintaining mental and physiological equilibrium. Individual assessment of Prakriti (constitution), Vikriti (current imbalance), Agni, and lifestyle can help guide a personalized Ayurvedic approach.

Pathogenesis of Seasonal Affective Disorder

From an Ayurvedic viewpoint, the development of seasonal mood disturbance may be conceptualized as a Samprapti (disease process) arising from an incompatibility between the individual’s internal state and recurring seasonal influences. Kala (time) and Ritu (season) can modify Dosha activity and bodily functions, while disruption of Ritucharya (seasonal regimen) may interfere with the body’s natural adaptation. In susceptible individuals, this may initiate Dosha Vaishamya (functional imbalance), followed by disturbance in the normal functions of Manas (mind). Predominance of Tamas may manifest as mental inertia and reduced engagement, whereas disturbed Rajas may interfere with emotional steadiness and mental organization. Continued imbalance can affect Manovaha Srotas, producing dysfunction in the pathways responsible for mental activity and emotional regulation. If these changes persist, Dhi (intellectual discrimination), Dhriti (mental restraint), and Smriti (memory) may become functionally impaired, influencing motivation, decision-making, and adaptation to routine activities.

Herbal Remedies for Seasonal Affective Disorder by Planet Ayurveda

Planet Ayurveda is a well-established Ayurvedic healthcare organization that works to promote the ancient knowledge of Ayurveda through natural remedies and holistic health solutions. The company develops a wide range of herbal formulations using pure, high-quality ingredients and standardized herbal extracts, with a focus on maintaining safety, authenticity, and effectiveness. Following the principles of classical Ayurveda, Planet Ayurveda aims to support overall health by addressing the underlying causes of health concerns and encouraging balance in the body, mind, and emotions. With an emphasis on quality, natural ingredients, and traditional approaches supported by modern research, the organization works toward making Ayurvedic wellness solutions available globally. We will explore various herbal approaches used for the management of Seasonal Affective Disorder according to Ayurvedic principles. The herbal formulations are:

  1. Neurogenie Capsules
  2. Ashwagandha Capsules
  3. Calm Easy Tea

Product description

1. Neurogenie Capsules

These contain Brahmi (Bacopa monnieri) and Ashwagandha (Withania somnifera), two traditionally used Ayurvedic herbs associated with mental and nervous-system support. In the context of Seasonal Affective Disorder, this formulation may be considered as a supportive Ayurvedic approach for maintaining mental balance, coping with stress, and supporting healthy sleep and cognitive function during seasonal changes. Brahmi is traditionally valued as a Medhya Rasayana (cognitive rejuvenative), while Ashwagandha is regarded as a Rasayana with adaptogenic properties.

Dosage: 2 capsules twice a day after meals with plain water.

2. Ashwagandha Capsules

These contain Ashwagandha (Withania somnifera), an Ayurvedic Rasayana (rejuvenative herb) traditionally used to support resilience, mental balance, and overall wellbeing. In the context of Seasonal Affective Disorder, Ashwagandha may be considered as a supportive Ayurvedic option for individuals experiencing stress, disturbed sleep, low energy, or difficulty adapting to seasonal changes. Its traditional use is particularly associated with promoting calmness and supporting healthy nervous-system function.

Dosage: 1 capsule twice a day after meals with plain water.

3. Calm Easy Tea

It contains a combination of Ashwagandha (Withania somnifera), Brahmi (Bacopa monnieri), Licorice (Glycyrrhiza glabra), Green Tea (Camellia sinensis), Ginger (Zingiber officinale), and Cinnamon (Cinnamomum verum). In an Ayurvedic supportive approach to Seasonal Affective Disorder, this herbal tea may be incorporated into a wellness routine aimed at maintaining mental calmness, relaxation, and daily balance during seasonal changes. Ashwagandha and Brahmi are traditionally valued for supporting mental wellbeing, while ginger and cinnamon are traditionally used to support digestion. Green tea provides a mild source of caffeine and antioxidants.

Dosage: 1 cup daily.

Dietary Tips for Seasonal Affective Disorder

The foods which can be included in the diet are as follows:

  • Green leafy vegetables: Kale, spinach and similar greens supply folate and other micronutrients that support overall brain health.
  • Whole grains: Oats, barley, and quinoa provide B-group vitamins that contribute to normal nervous-system function.
  • Dairy foods: Fresh milk, curd, and other dairy products can provide protein, calcium, and other nutrients as part of a balanced diet.
  • Nuts and seeds: Almonds, flaxseeds, and other nuts and seeds offer healthy fats, including plant-based omega-3 fatty acids, along with minerals that support neurological health.
  • Fruits: Avocados, berries, and other nutrient-dense fruits provide vitamins, minerals, fiber, and antioxidant compounds that contribute to overall wellbeing.

The foods to avoid in this disorder include:

  • Highly processed foods and added sugars: Frequent intake may cause rapid fluctuations in blood glucose and energy levels, which can affect overall mood and wellbeing.
  • Excessive caffeine and alcohol: High caffeine intake may interfere with sleep, while alcohol can disrupt normal sleep quality and emotional balance.
  • Excessively spicy foods: Very spicy meals may aggravate Pitta and, in susceptible individuals, contribute to digestive discomfort and imbalance of Vata.
  • Heavy and excessively fatty meats: These may feel difficult to digest and, from an Ayurvedic perspective, can aggravate Kapha, contributing to heaviness and sluggishness.
  • Stale or repeatedly reheated foods: Ayurveda recommends favoring freshly prepared meals, as stale foods may be considered less supportive of balanced digestion.

Conclusion

Early recognition, regular monitoring, and an individualized care plan are important for maintaining emotional wellbeing and preventing seasonal disturbances from affecting daily life. Consistent sleep, balanced nutrition, physical activity, adequate daylight exposure, meaningful social interaction, and appropriate psychological support can contribute to better overall functioning. Preventive strategies may also be considered when a recurring seasonal pattern is established. From an Ayurvedic perspective, following Ritucharya (seasonal regimen), supporting Agni (digestive and metabolic function), and promoting Sattva (mental clarity and stability) may offer complementary support for maintaining balance through seasonal transitions.