
Herbal Remedies of Psoriatic Arthritis – Causes, Symptoms, Diagnosis & Treatment

ABSTRACT

Psoriatic arthritis (PsA) is a chronic inflammatory condition that affects the joints and may occur along with psoriasis. It develops when the immune system becomes overactive and triggers inflammation in different parts of the musculoskeletal system. Patients may experience joint pain, swelling, morning stiffness, tenderness, and difficulty moving, while some also develop swelling of entire fingers or toes and discomfort around tendons. The pattern and severity can differ greatly between individuals. If persistent inflammation remains uncontrolled, structural changes and loss of joint function may occur. Early identification and appropriate management are important for maintaining mobility and quality of life. A comprehensive approach may include medical treatment, physical activity, weight management, balanced nutrition, stress control, and supportive therapies. Understanding the connection between skin, immune activity, and joint health can help in developing a more personalized approach to long-term care.
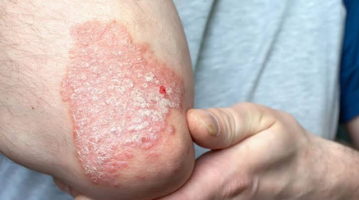
 Psoriatic Arthritis

INTRODUCTION TO PSORIATIC ARTHRITIS

Psoriatic arthritis (PsA) is a long-term inflammatory joint condition that can develop in people with psoriasis, a skin disorder characterized by red, scaly patches. Unlike ordinary wear-and-tear arthritis, PsA involves an abnormal immune response that can affect the joints, tendons, ligaments, fingers, toes, and spine. It may cause pain, stiffness, swelling, and reduced movement, with symptoms often varying from person to person. Some individuals develop joint problems before noticeable skin changes, making early recognition important.The disease can gradually damage affected joints if persistent inflammation is not adequately controlled. Psoriatic arthritis is therefore more than a skin-related problem—it is a systemic inflammatory disorder requiring attention to both musculoskeletal and overall health.

MECHANISM OF ACTION

Psoriatic arthritis (PsA) is a chronic immune-mediated inflammatory arthritis associated with psoriasis. The process begins with abnormal activation of the immune system, particularly involving dendritic cells, T cells, and inflammatory cytokines such as TNF-α, IL-17, and IL-23. The IL-23/IL-17 pathway plays an important role in maintaining inflammation at the joints, entheses (where tendons and ligaments attach to bone), and skin. These inflammatory signals stimulate synovial cells and other tissues, leading to synovitis, swelling, pain, and stiffness. At the same time, inflammation at the entheses can cause enthesitis, while chronic inflammation can promote both bone erosion and abnormal new bone formation. This combination of tissue inflammation, bone damage, and new bone growth contributes to the characteristic joint changes and reduced mobility seen in PsA.
The mechanism can be summarized as:inflammatory cytokine → receptor activation

cytokine signal
↓
jak activation
↓
stat activation
↓
nuclear signaling
↓
inflammatory gene expression
↓
inflammatory response
with jak1 inhibition

↓
reduced jak1-mediated signaling
↓
reduced downstream cytokine signaling
↓
lower inflammatory activity.

SYMPTOMS OF PSORIATIC ARTHRITIS

JOINT PAIN AND SWELLING

Peripheral arthritis is one of the most common manifestations. Patients may notice tenderness, swelling, warmth, or difficulty moving affected joints. hands and feet may be particularly troublesome, although knees, ankles, wrists, and other joints can also become involved.The pattern may be asymmetric or affect multiple joints on both sides of the body. 

MORNING STIFFNESS

Inflammatory Stiffness is often more noticeable after prolonged rest.

ENTHESITIS

Enthesitis refers to inflammation where tendons, ligaments, or fascia attach to bone.Commonly affected areas include:

  • Achilles Tendon
  • Plantar Fascia
  • Knees
  • Elbows
  • Pelvic Attachment Sites.

DACTYLITIS

Dactylitis produces diffuse swelling of an entire finger or toe, giving the digit a characteristic enlarged appearance.It results from inflammation involving several structures simultaneously, including joints, tendon sheaths, and surrounding tissues.

AXIAL SYMPTOMS

Some individuals develop inflammation affecting the spine or sacroiliac joints.

SKIN MANIFESTATIONS

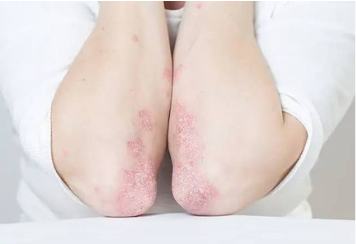
Psoriasis may appear as well-defined plaques covered with scales. The scalp, elbows, knees, trunk, and other areas can be involved.

NAIL CHANGES

  • Nail involvement may include:
  • Pitting
  • Ridging
  • Thickening
  • Discoloration
  • Separation of the nail from its bed

FATIGUE AND FUNCTIONAL DIFFICULTIES

Chronic inflammation can be associated with fatigue and reduced physical capacity. Difficulty opening containers, writing, walking, exercising, climbing stairs, or performing occupational tasks may develop when disease activity remains uncontrolled.

INVESTIGATIONS FOR PSORIATIC ARTHRITIS

There is no single blood test that independently confirms psa. diagnosis is based on the clinical picture, physical examination, medical history, psoriasis status, musculoskeletal findings, laboratory assessment, and imaging when necessary.

CLINICAL EVALUATION

  • The first investigation is a detailed clinical assessment.
  • Number And Distribution Of Tender Joints.
  • Number Of Swollen Joints.
  • Presence Of Dactylitis.
  • Enthesitis Sites.
  • Spinal Mobility.
  • Sacroiliac Symptoms.
  • Nail Abnormalities.
  • Extent Of Psoriasis.
  • Functional Limitations.
  • Previous Episodes Of Inflammatory Disease.

BLOOD INVESTIGATIONS

Blood tests in psoriatic arthritis (PsA) mainly help assess inflammation, anemia, and exclude other types of arthritis.

COMPLETE BLOOD COUNT

Hemoglobin (Hb): May be decreased, particularly with chronic inflammation, resulting in anemia of chronic disease. Total Leukocyte Count (TLC/WBC)-May be normal or mildly increased due to systemic inflammation. Platelet Count (PLT): Can be increased (thrombocytosis) during active inflammation; it may remain normal in mild or controlled disease.

ESR

Erythrocyte sedimentation rate can provide an indirect indication of systemic inflammatory activity.

CRP

C-Reactive Protein Is Another Marker Used To Assess Inflammation.

RHEUMATOID FACTOR

Rheumatoid Factor May Be Measured When Rheumatoid Arthritis Is Part Of The Differential Diagnosis. PSA  Is Commonly Seronegative For Rheumatoid Factor.

ANTI-CCP ANTIBODIES

Anti-Cyclic Citrullinated Peptide Antibodies May Also Help Distinguish Rheumatoid Arthritis From Psa In Appropriate Clinical Situations.

X-RAY

  • Conventional Radiography Can Demonstrate Structural Changes Such As:
  • Erosions
  • Joint-Space Alterations
  • New Bone Formation
  • Ankylosis
  • Other Chronic Changes

ULTRASOUND

Musculoskeletal Ultrasound Can Identify:

  • Synovitis
  • Tendon Sheath Inflammation
  • Enthesitis
  • Increased Blood Flow Associated With Active Inflammation.

DIFFERENTIAL DIAGNOSIS

Because Several Diseases Can Produce Joint Pain And Swelling, Psa Must Be Differentiated From Other Inflammatory And Musculoskeletal Disorders.Important Possibilities Include:

  • Rheumatoid Arthritis
  • Osteoarthritis
  • Gout
  • Reactive Arthritis
  • Ankylosing Spondylitis And Related Spondyloarthritis

AYURVEDIC PERSPECTIVE OF PSORIATIC ARTHRITIS

Psoriatic arthritis (psa) does not have a single, exact equivalent in the classical ayurvedic texts. Its combination of chronic skin lesions and inflammatory musculoskeletal manifestations can be understood through overlapping ayurvedic concepts, particularly kushtha (chronic skin disorders), vatarakta (vata-rakta disorder), and amavata (ama-associated joint disorder), depending upon the patient’s individual presentation. Therefore, an ayurvedic correlation should be based on the dominant dosha (functional biological principle), Dhatu (body tissue), Srotas (physiological channel), agni (digestive and metabolic capacity), and ama (incompletely processed metabolic material) rather than assigning every patient to one classical diagnosis.

The skin component may be considered in relation to Twak (skin) and Rakta Dhatu (blood tissue), while pain, stiffness, swelling, and restricted joint movement indicate involvement of sandhi (joints) and predominantly vata dosha. kapha may contribute to heaviness, swelling, itching, and thickening. Thus, the ayurvedic picture may involve a combination of vata-kapha imbalance, rakta involvement, impaired agni, and ama, with the exact pattern varying from person to person.

The ayurvedic pathogenesis may begin with Mithya ahara-vihara (improper diet and lifestyle), irregular eating, excessive heavy food, unsuitable food combinations, sedentary habits, inadequate sleep, chronic stress, or other individual triggers.

These factors may disturb agni (digestive and metabolic function).
agni dushti (impaired digestion and metabolism)
↓
ama utpatti (formation of ama)
↓
dosha prakopa (aggravation of doshas)
↓
srotodushti (disturbance of body channels)
↓
rakta and twak involvement (skin-related manifestation)
↓
vata involvement in sandhi (joint localization)
↓

sandhi shoola + shotha + stambha
(joint pain + swelling + stiffness

  • NIDANA PARIVARJANA – AVOIDANCE OF CAUSATIVE FACTORS- The first principle is to identify and reduce factors that aggravate the patient’s condition.This may include:
  • irregular meals
  • overeating
  • excessively heavy food
  • highly processed foods
  • excessive sedentary behavior
  • poor sleep routine
  • excessive stress
  • individually identified dietary triggers
  • AGNI DEEPANA – SUPPORTING DIGESTIVE FUNCTION- When impaired digestion is present, treatment may emphasize agni deepana (supporting digestive capacity).
  • AMA PACHANA –When the clinical picture indicates ama, ama pachana (supporting the processing and reduction of ama) may form part of the treatment strategy.
  • DHATU SUPPORT – TISSUE NOURISHMENT-Chronic musculoskeletal disease requires attention to asthi dhatu (bone tissue), mamsa dhatu (muscle tissue), majja dhatu (marrow/deeper tissue concept), and rakta dhatu (blood tissue) according to the patient’s presentation.

HERBAL REMEDIES FOR PSORIATIC ARTHRITIS  BY PLANET AYURVEDA

Planet Ayurveda is an Ayurvedic wellness brand focused on providing herbal formulations based on the principles of Ayurveda (traditional Indian system of medicine). The brand offers a range of products prepared using herbs, herbal extracts, classical Ayurvedic ingredients, and traditional formulations.  Planet Ayurveda emphasizes the traditional Ayurvedic concepts of Dosha balance, Agni (digestive fire), Dhatu nourishment (tissue health), and natural herbal support. Products are presented as supportive wellness options and are intended to complement healthy lifestyle practices. Individual products should be selected according to the person’s condition and used appropriately, particularly when someone has a diagnosed medical condition or is taking conventional medicines.Here, we will discuss  formulations used for psoriatic arthritis.

  1. Boswellia-Curcumin
  2. Yograj Guggul
  3. Coral Calcium Complex
  4. Bone Support

Herbal Remedies For Psoriatic Arthritis

Buy Now Herbal Remedies For Psoriatic Arthritis

Buy Now Herbal Remedies Psoriatic Arthritis

PRODUCT DESCRIPTION

1. Boswellia–Curcumin

Boswellia–Curcumin combines two well-known herbs, Shallaki (Boswellia serrata) and Haridra (Curcuma longa), traditionally used for Shotha (inflammation) and Sandhi Shoola (joint pain). Shallaki supports a balanced inflammatory response and may help reduce Sandhi Shotha (joint swelling), stiffness, and discomfort.its resin contains boswellic acids, which have been investigated for their effects on inflammatory pathways. Haridra is valued for its Shothahara (anti-inflammatory) and Vedanasthapana (pain-relieving) properties and provides antioxidant support. its major bioactive constituent, curcumin, has been investigated for interactions with multiple inflammatory pathways.Together, they may support comfortable joint movement and help maintain Sandhi Bala (joint strength), making them useful as supportive care for inflammatory joint conditions such as psoriaticArthritis.

Dosage -1 Capsule Twice Daily .

2. Yograj Guggulu

Yograj guggulu is a classical ayurvedic formulation prepared using Guggul (Commiphora mukul) etc traditionally used in disorders involving vata dosha and the musculoskeletal system.it is traditionally considered in presentations involving:sandhi shoola (joint pain),sandhi stambha (joint stiffness),reduced mobility,vata-associated musculoskeletal discomfort.Its role can be understood within the broader ayurvedic strategy of supporting normal vata function and musculoskeletal mobility.

Dosage -1 Tablet Twice A Day.

3. Coral Calcium Complex

Coral calcium Complex capsules is used as a nutritional component of a bone-support strategy prepared using Guduchi (Tinospora Cordifolia), Kamdudha Ras etc. In ayurvedic terminology, Asthi dhatu (bone tissue) is responsible for maintaining the skeletal framework of the body. Adequate nutritional support is important for maintaining normal bone mineralization.This combination brings together Pitta-Shamana (Pitta-balancing), Daha-Shamana (relief of burning/heat), Rasayana (rejuvenative support), and Dhatu Poshan (tissue nourishment) concepts.

Dosage – 1 Capsule Twice Daily .

4. Bone support

Bone support capsules by Planet Ayurveda are prepared using Arjuna (Terminalia arjuna), Hadjod (Cissus Quadrangularis) etc. A bone support formulation can be incorporated into an ayurvedic supportive program when maintaining skeletal health is an important objective.Ayurveda considers asthi dhatu as an important component of the musculoskeletal system,while modern medicine recognizes the importance of adequate calcium, vitamin d, protein, physical activity, and muscle strength for skeletal health.

Dosage– 1-2 Capsule Twice Daily.

DIET FOR PSORIATIC ARTHRITIS

According to Ayurveda, dietary planning in Psoriatic Arthritis can focus on balancing aggravated Vata and Pitta Dosha, reducing Ama (metabolic waste/undigested material), supporting Agni (digestive fire), and avoiding foods that may promote Shotha (inflammation).
Recommended Foods

  • Laghu Ahara (light food): Prefer easily digestible meals such as Yavagu (thin rice porridge), Mudga Yusha (moong dal soup), Khichadi, and vegetable soups.
  • Mudga (green gram): Light and relatively easy to digest; useful when Agni is weak.
  • Shali Dhanya (old rice): Traditionally considered light and suitable for regular meals.
  • Yava (barley): Can be included in moderation as a Laghu and Kapha-reducing grain.
  • Tikta Shaka (bitter vegetables): Vegetables such as Patola (pointed gourd), Karela (bitter gourd), and leafy greens may be included according to individual tolerance.
  • Drava Ahara (liquid foods): Warm soups and thin preparations can be useful when digestion is weak.
  • Ushna Jala (warm water): Prefer warm or comfortably hot water instead of frequent chilled beverages.
  • Haridra (turmeric): May be incorporated into food as a traditional Shothahara (inflammation-supporting) spice.
  • Shunthi (dry ginger): Used traditionally to support Agni Deepana (digestion stimulation) and reduce Ama.
  • Jeeraka (cumin): Can be used in cooking to support Deepana-Pachana (digestive function).
  • Dhaniya (coriander): May be used as a mild digestive spice, particularly when Pitta is prominent.

FOODS TO LIMIT

  • Guru Ahara (heavy foods): Excessive fried, greasy, and very rich foods may be difficult to digest and can contribute to Ama formation.
  • Abhishyandi Ahara (foods that promote obstruction/kapha accumulation): Excessive curd, cheese, cream, and very heavy dairy preparations should be limited, especially when there is Kapha or Ama predominance.
  • Dadhi (curd/yogurt): Ayurveda traditionally advises caution with frequent or excessive curd consumption, particularly in inflammatory and Kapha-associated conditions.
  • Madhura Ati-Sevana (excessive sweet foods): Reduce sweets, sugary beverages, desserts, and highly processed foods.
  • Ati-Lavana (excess salt): Avoid excessive salty and packaged foods.
  • Amla Ahara (excessively sour foods): Limit very sour, pickled, and fermented foods when Pitta is aggravated.
  • Katu Ahara (excessively pungent foods): Very spicy foods may aggravate Pitta in susceptible individuals.
  • Viruddha Ahara (incompatible food combinations): Avoid traditionally incompatible combinations, particularly Dadhi with certain foods and other combinations that are poorly tolerated.
  • Guru-Mamsa (heavy meats): Excessive intake of heavy, fatty meat preparations should be avoided when digestion is weak.
  • Madya (alcohol): Avoid or minimize alcohol, as it may aggravate inflammatory symptoms and is traditionally considered unsuitable in many inflammatory conditions.

CONCLUSION

Psoriatic arthritis can be interpreted as a complex disorder involving dosha imbalance, impaired agni, ama, rakta and twak involvement, and vata-related disturbance of sandhi, with the exact presentation differing between individuals. The combination of skin manifestations and musculoskeletal symptoms makes individualized assessment especially important.The ayurvedic strategy therefore extends beyond the use of a single formulation. it may involve nidana parivarjana (removal of causative factors), agni deepana (supporting digestion), ama pachana (addressing ama), dosha shamana (pacifying aggravated doshas), appropriate diet and dinacharya (daily routine), physical activity, and selected supportive formulations.Within this framework, boswellia-curcumin may be positioned for joint and inflammatory support, yograj guggulu for traditional vata-related musculoskeletal support, coral calcium for calcium supplementation and skeletal nutrition, and bone support for maintaining overall bone health.A responsible integrative approach therefore combines appropriate rheumatological disease control with individualized ayurvedic lifestyle and supportive measures, while ensuring that potential herb–drug interactions, contraindications, product quality, and ongoing disease activity are reviewed by qualified healthcare professionals.

Upadoz / Upadacitinib and Psoriatic Arthritis: Targeting Inflammation at Its Source

Abstract

Psoriatic arthritis (PsA) is a chronic inflammatory condition characterized by persistent joint inflammation, pain, stiffness, and progressive structural damage, often occurring alongside psoriasis. Upadacitinib (Upadoz) represents a targeted therapeutic approach that acts primarily through inhibition of Janus kinase 1 (JAK1), a key intracellular pathway involved in cytokine-mediated inflammatory signaling. By interfering with JAK–STAT signaling, upadacitinib can reduce downstream inflammatory activity and help control multiple manifestations of PsA. Clinical studies, including the SELECT-PsA trials, have demonstrated improvements in joint symptoms, physical function, and other disease manifestations among appropriately selected patients. Its oral once-daily administration also provides a convenient treatment option

Upadoz / Upadacitinib and Psoriatic Arthritis

Statistics for Psoriatic Arthritis

  • Psoriatic arthritis affects around 0.1%–0.2% of the worldwide population.
  • Estimates place the prevalence at approximately 112–130 cases per 100,000 adults.
  • Around 3–41 new cases per 100,000 person-years are reported globally.
  • Rates tend to be higher in Europe and North America than in Asia and South America.
  • Nearly 1 in 5 people with psoriasis may eventually develop psoriatic arthritis.
  • Studies report considerable variation, with approximately 6%–41% of psoriasis patients developing joint disease.
  • In about 68% of cases, psoriasis develops before arthritis symptoms.
  • Approximately 15% experience skin and joint manifestations around the same time.
  • About 17% develop joint symptoms before noticeable skin lesions.

Interesting Facts about Psoriatic Arthritis

  • Skin and joints are connected: Psoriatic arthritis can affect both the skin and musculoskeletal system, although joint disease may sometimes occur without obvious psoriasis.
  • Different people show different patterns: Psoriatic arthritis does not follow one fixed pattern, which can make diagnosis challenging.
  • It is not simply “wear and tear”: Unlike osteoarthritis, PsA is an immune-mediated inflammatory arthritis.
  • Arthritis can precede psoriasis: In a minority of patients, joint inflammation appears before any visible skin lesions, sometimes making the diagnosis difficult.
  • The jaw can be affected: PsA may involve the temporomandibular joint (TMJ), potentially causing jaw pain, stiffness, or difficulty opening the mouth.
  • Hidden inflammation may exist despite limited skin disease: The severity of psoriasis on the skin does not necessarily reflect the extent of underlying musculoskeletal involvement.
  • It can mimic several other conditions: Depending on the joints and tissues involved, PsA may resemble rheumatoid arthritis, gout, osteoarthritis, or other spondyloarthropathies, making clinical pattern recognition important.

Introduction

Psoriatic arthritis (PsA) is a heterogeneous, chronic inflammatory musculoskeletal disease associated with psoriasis and characterized by involvement of peripheral joints, entheses, digits, and axial structures. The underlying immunopathology involves a complex network of cytokines and intracellular signaling pathways that sustain synovial inflammation, enthesitis, osteoproliferation, and bone erosion. Persistent inflammatory activity may consequently result in functional impairment, structural joint damage, and deterioration in quality of life. The clinical heterogeneity of PsA also presents challenges in achieving comprehensive disease control, particularly when multiple domains of disease activity coexist. Advances in understanding the molecular mechanisms underlying PsA have facilitated the development of targeted synthetic disease-modifying antirheumatic drugs (tsDMARDs). Among these, upadacitinib (Upadoz) is an orally administered, selective Janus kinase 1 (JAK1) inhibitor designed to interfere with intracellular cytokine signaling. JAK1 participates in signal transduction mediated by several cytokines implicated in PsA pathogenesis, including pathways associated with interleukin and interferon activity. Pharmacological inhibition of JAK1 therefore provides a mechanism for attenuating multiple inflammatory signals simultaneously.

Causes and Risk Factors of Psoriatic Arthritis

Psoriatic arthritis does not have a single identifiable cause. It is believed to develop through an interaction between genetic susceptibility, immune dysregulation, and environmental or mechanical triggers.

Genetic predisposition

A family history of psoriasis or PsA increases susceptibility. Several genetic variants, particularly within immune-regulatory genes, have been associated with disease development.

Immune-system dysregulation

 Abnormal activation of immune pathways promotes the release of inflammatory mediators, including TNF-α, IL-17, and IL-23, contributing to joint and entheseal inflammation.

Psoriasis

The presence of cutaneous or nail psoriasis is the strongest established clinical risk factor for developing PsA, although arthritis can occasionally precede skin manifestations.

Environmental triggers

Infections, physical trauma, psychological stress, and other environmental influences may contribute to disease onset or flare in genetically predisposed individuals.

Joint or tissue injury

Mechanical stress or previous trauma may initiate inflammation at susceptible sites, particularly around entheses.

Obesity and metabolic factors

Excess adiposity is associated with an increased likelihood of PsA and may also contribute to greater inflammatory activity.

Smoking and lifestyle factors

Tobacco exposure and certain lifestyle-related factors have been investigated as potential modifiers of PsA risk and disease severity.

Gut–immune interactions

Alterations in the intestinal microbiome and mucosal immune responses are being investigated for their possible contribution to PsA development.

Signs and Symptoms of Psoriatic Arthritis

Psoriatic arthritis can present differently from one person to another. The pattern and intensity of symptoms may also change over time. The symptoms include:

Joint pain and tenderness

Affected joints may become painful, particularly during movement or prolonged activity. Tenderness can occur around the joint as well as in the surrounding tissues.

Joint swelling

Inflammation may cause visible swelling and a feeling of fullness around affected joints. Swelling can involve one or several joints.

Morning stiffness

Stiffness after waking or following prolonged inactivity is common. It may persist for some time and often improves as the joints become mobile.

Reduced range of motion

Inflammation, pain, and swelling can restrict normal joint movement, affecting activities such as walking, gripping, climbing stairs, or bending.

Dactylitis

 An entire finger or toe may become diffusely swollen because inflammation involves multiple structures within the digit. This characteristic presentation is often described as a “sausage digit.”

Enthesitis

Inflammation can occur where tendons or ligaments attach to bone. Common sites include the heel, achilles tendon, sole of the foot, and elbow, producing localized pain and tenderness.

Lower back or spinal symptoms

Some individuals develop inflammatory back pain involving the spine or sacroiliac joints. Stiffness may be more noticeable after rest and may improve with physical activity. .

Psoriatic skin lesions

Red, scaly, well-defined plaques may occur, commonly affecting the scalp, elbows, knees, or other areas.

Knee, ankle, or other large-joint involvement

PsA may affect larger peripheral joints, producing swelling, pain, stiffness, and functional limitations.

Asymmetrical joint involvement

 Unlike some other inflammatory arthritides, PsA may affect different joints on opposite sides of the body, although symmetrical patterns can also occur.

Episodes of worsening

Symptoms may fluctuate, with periods of increased inflammation or flares followed by periods when symptoms become less pronounced.

Progressive functional impairment

Persistent untreated inflammation can eventually interfere with mobility, hand function, work, exercise, and other everyday activities.

Nail abnormalities

Psoriatic arthritis may be accompanied by nail pitting, ridging, discoloration, thickening, crumbling, or separation of the nail from its underlying bed.

How Upadoz Works for the Management of Psoriatic Arthritis

Upadoz (upadacitinib) is a targeted oral therapy belonging to the Janus kinase (JAK) inhibitor class. Its principal pharmacological action is directed toward JAK1, an intracellular kinase involved in transmitting signals generated by several cytokines implicated in immune-mediated inflammation. Rather than neutralizing a cytokine outside the cell, upadacitinib interferes with the intracellular signaling machinery responsible for translating cytokine–receptor interactions into cellular responses.

Inhibition of JAK–STAT signaling

Following cytokine binding to its cellular receptor, JAK proteins become activated and phosphorylate signal transducers and activators of transcription (STATs). Activated STATs subsequently influence gene transcription within the nucleus, promoting immune-cell activation and inflammatory responses. Upadacitinib inhibits JAK activity and thereby reduces STAT phosphorylation and downstream transcriptional signaling.

Preferential JAK1 activity

Upadacitinib demonstrates greater inhibitory potency toward JAK1 than JAK2, JAK3, and TYK2. This pharmacological selectivity is relevant because JAK1 participates in signaling pathways associated with several inflammatory cytokines. However, JAK selectivity should not be interpreted as complete exclusivity; cytokine receptors frequently utilize JAK combinations, allowing JAK1 inhibition to influence multiple signaling pathways.

Suppression of inflammatory signaling

Psoriatic arthritis involves dysregulated immune signaling that contributes to synovitis, enthesitis, dactylitis, and other inflammatory manifestations. By attenuating JAK-dependent cytokine signaling, upadacitinib can reduce the intracellular inflammatory response and consequently decrease disease activity.

Impact across multiple disease domains

The therapeutic significance of JAK1 inhibition extends beyond reduction of joint inflammation. Clinical studies of upadacitinib in PsA have demonstrated improvements in peripheral arthritis, physical function, enthesitis, dactylitis, and psoriasis-related manifestations, supporting its role as a treatment capable of addressing several domains of this heterogeneous disease.

Thus, Upadoz acts at an important intracellular signaling checkpoint, interrupting cytokine-driven communication before it culminates in sustained inflammatory activity. This targeted mechanism provides the pharmacological basis for its use in appropriately selected patients with active PsA.

Who May Benefit from Upadacitinib?

Upadacitinib may be considered for patients with active psoriatic arthritis (PsA) when conventional treatment does not provide adequate disease control or cannot be tolerated. Patient selection should be individualized according to disease severity, affected domains, previous therapies, comorbidities, and safety considerations.

Patients with active PsA despite DMARD therapy

Individuals who continue to experience clinically significant joint inflammation, pain, stiffness, or functional impairment despite disease-modifying antirheumatic drugs may be candidates for targeted therapy.

Patients with inadequate response to biologic therapy

Clinical evidence supports upadacitinib in patients whose PsA remains active despite treatment with one or more biologic DMARDs. SELECT-PsA 2 specifically evaluated this treatment setting and demonstrated significantly greater clinical responses than placebo.

Patients with inadequate response or intolerance to TNF inhibitors

Current U.S. prescribing information identifies active PsA with inadequate response or intolerance to one or more TNF blockers as an indication for upadacitinib.

Patients with multiple disease manifestations

Upadacitinib may be particularly relevant when PsA involves several domains simultaneously, such as peripheral arthritis, enthesitis, dactylitis, axial symptoms, and psoriasis. Clinical trials have demonstrated improvements across several of these manifestations.

Patients requiring an oral targeted treatment

Upadacitinib is administered orally once daily, providing an alternative to injectable biologic therapies for appropriately selected patients.

Patients requiring substantial disease control

Trial data have shown improvements in joint responses, physical function, psoriasis outcomes, and achievement of minimal disease activity, supporting its role in patients with clinically meaningful disease burden.

Importantly, upadacitinib is not appropriate for every patient with PsA. Before initiation, clinicians should evaluate infection risk, tuberculosis and viral hepatitis status where appropriate, blood counts, liver function, cardiovascular and thromboembolic risk, malignancy risk, pregnancy considerations, and potential drug interactions. The drug should also not be combined with other JAK inhibitors or biologic DMARDs. Therefore, the potential benefit of upadacitinib is greatest when its targeted mechanism, clinical profile, and safety considerations align with the individual patient’s disease characteristics and previous treatment history.

Ayurveda Insights

From an Ayurvedic perspective, psoriatic arthritis may be understood through the interplay of Vata and Pitta doshas with impaired Agni and accumulation of Ama, particularly when inflammatory manifestations involve the joints, skin, and soft tissues. The clinical picture may be considered in relation to Amavata when prominent features include pain, stiffness, swelling, and systemic inflammatory activity, while associated skin manifestations may reflect disturbances involving Rakta and Twak dhatus. Ayurvedic management focuses on identifying causative dietary and lifestyle factors, supporting Agni, reducing Ama, restoring doshic balance, and maintaining healthy tissue metabolism.

Pathogenesis of Psoriatic Arthritis

Ayurvedic interpretation of psoriatic arthritis can be developed through the concept of Samprapti, emphasizing the progression of pathological changes from the initial doshic disturbance to localization in specific tissues. Persistent exposure to causative factors may initiate Dosha Prakopa, followed by alteration of normal tissue nourishment and circulation. The disturbed Doshas subsequently gain access to susceptible Kha-Vaigunya (vulnerable sites), particularly the joints, tendons, and skin. Vata facilitates the movement and localization of the aggravated Doshas, while Pitta may intensify inflammatory and erythematous manifestations. In the musculoskeletal system, involvement of Sandhi, Asthi, and Majja, together with impaired function of Snayu, can account for pain, stiffness, swelling, and restricted movement. Concurrent involvement of Rakta and Twak provides an Ayurvedic framework for associated cutaneous manifestations.

Ayurvedic Alternatives for Upadoz/Upadacitinib by Planet Ayurveda

Planet Ayurveda is a well-established Ayurvedic healthcare organization that works to promote the ancient knowledge of Ayurveda through natural remedies and holistic health solutions. The company develops a wide range of herbal formulations using pure, high-quality ingredients and standardized herbal extracts, with a focus on maintaining safety, authenticity, and effectiveness. Following the principles of classical Ayurveda, Planet Ayurveda aims to support overall health by addressing the underlying causes of health concerns and encouraging balance in the body, mind, and emotions. With an emphasis on quality, natural ingredients, and traditional approaches supported by modern research, the organization works toward making Ayurvedic wellness solutions available globally. We will explore various herbal approaches used for the management of Psoriatic Arthritis  according to Ayurvedic principles. The herbal formulations are:

  1. Boswellia Curcumin
  2. Coral Calcium Complex
  3. Bone Support
  4. Yograj Guggul

Herbal Remedies For Psoriatic Arthritis

Buy Now Herbal Remedies For Psoriatic Arthritis

Buy NowHerbal Remedies For Psoriatic Arthritis

Product description

1. Boswellia Curcumin

These contain Brahmi (Bacopa monnieri) and Ashwagandha (Withania somnifera), two traditionally used Ayurvedic herbs associated with mental and nervous-system support. In the context of Seasonal Affective Disorder, this formulation may be considered as a supportive Ayurvedic approach for maintaining mental balance, coping with stress, and supporting healthy sleep and cognitive function during seasonal changes. Brahmi is traditionally valued as a Medhya Rasayana (cognitive rejuvenative), while Ashwagandha is regarded as a Rasayana with adaptogenic properties.

Dosage: 2 capsules twice a day after meals with plain water.

2. Coral Calcium Complex

These contain Ashwagandha (Withania somnifera), an Ayurvedic Rasayana (rejuvenative herb) traditionally used to support resilience, mental balance, and overall wellbeing. In the context of Seasonal Affective Disorder, Ashwagandha may be considered as a supportive Ayurvedic option for individuals experiencing stress, disturbed sleep, low energy, or difficulty adapting to seasonal changes. Its traditional use is particularly associated with promoting calmness and supporting healthy nervous-system function.

Dosage: 1 capsule twice a day after meals with plain water.

3. Bone Support

It contains a combination of Ashwagandha (Withania somnifera), Brahmi (Bacopa monnieri), Licorice (Glycyrrhiza glabra), Green Tea (Camellia sinensis), Ginger (Zingiber officinale), and Cinnamon (Cinnamomum verum). In an Ayurvedic supportive approach to Seasonal Affective Disorder, this herbal tea may be incorporated into a wellness routine aimed at maintaining mental calmness, relaxation, and daily balance during seasonal changes. Ashwagandha and Brahmi are traditionally valued for supporting mental wellbeing, while ginger and cinnamon are traditionally used to support digestion. Green tea provides a mild source of caffeine and antioxidants.

Dosage: 1 cup daily.

4. Yograj Guggul

It is a classical Ayurvedic polyherbal formulation containing Commiphora mukul (Guggulu), Plumbago zeylanica (Chitraka), Emblica officinalis (Amalaki), Cyperus rotundus (Musta), Terminalia bellirica (Bibhitaki), Piper longum (Pippali), Carum copticum, Tribulus terrestris, and several other botanicals. In Ayurvedic practice, its combination is traditionally used in disorders involving joint stiffness, pain, and impaired musculoskeletal function. The formulation may therefore provide supportive care for musculoskeletal symptoms associated with PsA, particularly discomfort and restricted mobility.

Dosage: 1 tablet twice a day with lukewarm water.

Conclusion

Upadacitinib has emerged as an important targeted option for achieving broader disease control in patients with active psoriatic arthritis. Its selective JAK1-directed activity provides a pharmacological means of interrupting several cytokine-dependent inflammatory pathways. Its oral administration may also offer practical advantages for appropriately selected patients. Overall, upadacitinib represents a significant advancement in targeted PsA management, particularly when sustained suppression of multidimensional inflammatory activity remains difficult to achieve.